Clinical Trials Market (2026 - 2035)

Clinical Trials Market Research Report: Size, Share, Trend Analysis By Phase (Phase I, Phase II, Phase III, Phase IV), By Study Design (Interventional, Observational, Expanded Access), By Therapeutic Area (Oncology, Cardiology, Neurology, Infectious Diseases, Endocrinology), By End Use (Pharmaceutical Companies, Biotechnology Companies, Contract Research Organizations) and By Regional (North America, Europe, South America, Asia Pacific, Middle East and Africa) - Growth Outlook & Industry Forecast Till 2035

Forecast Period
2026-2035
CAGR
6.05%
2025 Market Size
USD 84.11 Billion
2035 Market Size
USD 151.43 Billion
Healthcare ● Updated August 24, 2026 Report ID: MRFR/HC/6317-HCR | Pages: 200 | Author: Vikita Thakur, Rahul Gotadki

Clinical Trials Market Summary

The Clinical Trials Market reached USD 84.11 billion in 2025 and opens the forecast window at USD 89.25 billion in 2026, climbing to USD 151.43 billion by 2035 at a 6.05% CAGR. Two catalysts anchor that trajectory. The EU Clinical Trials Regulation, fully binding through the CTIS portal since January 2025, consolidated 27 national submissions into one dossier and pulled multi-country study starts forward. Meanwhile, the U.S. Inflation Reduction Act's Medicare negotiation timeline has pushed sponsors to compress evidence-generation cycles, redirecting roughly 14% of late-stage budgets toward faster readouts [1][3].

Paper case report forms and siloed site monitoring are a thing of the past. Now electronic data capture, risk-based monitoring engines and wearable-fed endpoint collection do the heavy lifting. Instead of replacing traditional site networks altogether, sponsors have built decentralized components on top of them. In 2023–2025, venture and corporate investment in trial-technology vendors surpassed USD 4.8 billion, and the FDA’s final guidelines on decentralized trials provided sponsors with regulatory assurance to expand hybrid procedures across pivotal programs [2][7].


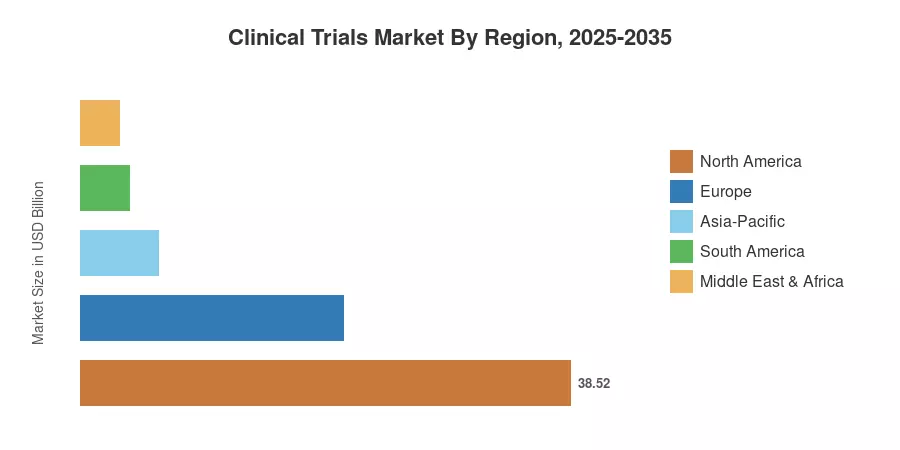
Geography still counts in economics. North America dominates the Clinical Trials Market, holding a 45.8% share, bolstered by robust investigator networks and yearly NIH funding of over USD 47 billion. The Asia-Pacific region is growing fastest at 7.34% CAGR, with Chinese and Indian regulators approving protocols in about 30 days. Europe comes next with 24.6%, and its momentum is linked to the harmonization of CTIS. The coming decade will reward operators that can translate speed into enrollment assurance.


Key Report Takeaways

• By Study Phase

  • Phase III studies held a 51.2% share of the Clinical Trials Market in 2025, reflecting the concentration of spend in pivotal registration programs.
  • Phase II is advancing at a 6.32% CAGR as biomarker-driven proof-of-concept work absorbs larger budgets.


• By Service

  • Clinical trial monitoring accounted for 26.5% of total service spend in 2025
  • Decentralized service delivery is the fastest-growing line item at 13.58% CAGR through 2035


• By Geography

  • North America generated USD 38.52 billion in 2025
  • Asia-Pacific is projected to grow at 7.34% CAGR through 2035
  • Europe accounted for 24.6% of global revenue in 2025


Market Size and Forecast (2021–2035)

Estimates are derived from sponsor R&D disclosures of the top 40 pharmaceutical filers, contract research organization segment reporting, registry activity recorded on ClinicalTrials.gov and the WHO ICTRP, and per-patient cost benchmarks triangulated based on Tufts CSDD study economics. Historical values are rebased to constant 2025 dollars, and projection values are based on protocol volume-growth vs inflation-adjusted per-study cost curves.
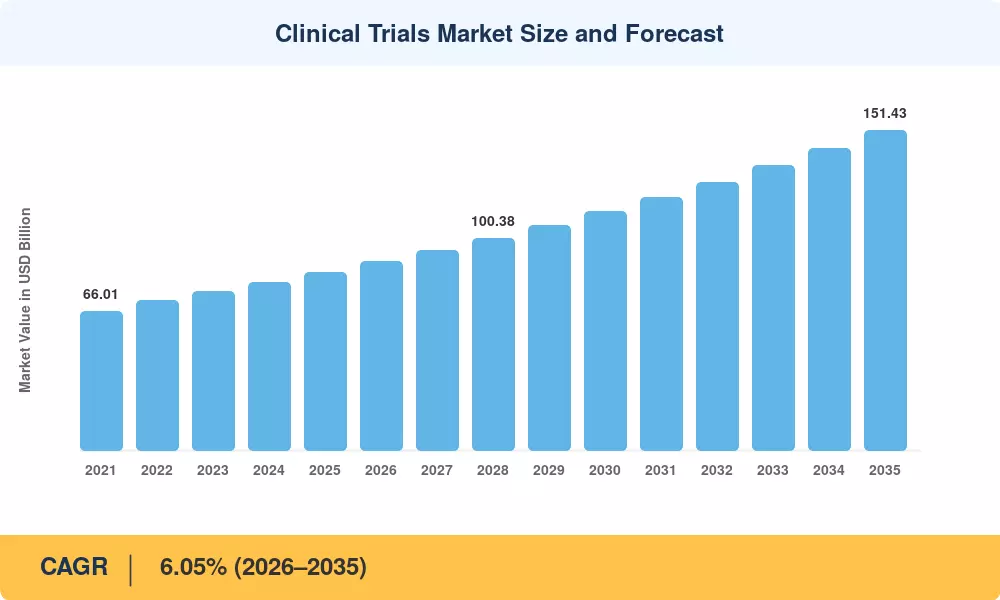
Clinical Trials Market Size and Forecast
Our Impact
Enabled $4.3B Revenue Impact for Fortune 500 and Leading Multinationals
Partnering with 2000+ Global Organizations Each Year
30K+ Citations by Top-Tier Firms in the Industry

Driver Impact Analysis

Driver ~% Impact on CAGR Geographic Relevance Impact Timeline
Oncology and rare-disease pipeline expansion ~1.5% Global Long-term (≥4 yr)
Regulatory harmonization (CTIS, ICH E6(R3)) ~1.1% Europe, Japan Medium-term (2–4 yr)
Decentralized and hybrid protocol adoption ~0.9% North America, Europe Medium-term (2–4 yr)
AI-enabled site selection and screening ~0.8% Global Long-term (≥4 yr)
Asia-Pacific enrollment cost arbitrage ~0.7% Asia-Pacific Short-term (≤2 yr)
Biosimilar and generic comparative studies ~0.6% Europe, Asia-Pacific Short-term (≤2 yr)
Real-world evidence integration into regulatory dossiers ~0.5% North America Long-term (≥4 yr)


Oncology Pipeline Density

Cancer programs consume more protocol capacity than any other therapeutic category, and the pipeline keeps thickening. The FDA authorized 50 novel therapeutics in 2024, with oncology accounting for roughly a third of approvals, each supported by multi-arm registration programs that routinely exceed USD 300 Million in cumulative study cost [5][6]. Antibody-drug conjugates and bispecifics complicate matters further: they require dose-optimization work under Project Optimus, adding a randomized dose-comparison stage that did not exist five years ago. Sponsors have responded by expanding Phase II budgets rather than shortening them.

Regulatory Harmonization in Europe

Since January 2025, every interventional study in the European Union runs through CTIS, ending the parallel national-submission era. Sponsors report median assessment timelines near 106 days for standard applications, against the 200-plus days multi-country programs previously absorbed [1]. The revised ICH E6(R3) good clinical practice guideline, adopted in 2025, formally endorses risk-proportionate monitoring, which lets sponsors reallocate roughly 18% of monitoring hours to centralized statistical surveillance [8].

Decentralized Execution and Enrollment Reach

Hybrid designs widen the catchment radius around each site. The FDA's decentralized-trial guidance, finalized in September 2024, clarified sponsor obligations for remote consent, local laboratory use, and direct-to-participant drug shipment [2]. Sponsors deploying these components across cardiometabolic programs report screening-to-randomization improvements of 20–25% and meaningful reductions in the 30% dropout rates that historically plagued long-duration studies [12].

Artificial Intelligence in Feasibility and Screening

Machine-learning models trained on electronic health records now pre-screen eligible participants before a coordinator opens a chart. IQVIA and Nvidia announced a joint agentic-AI initiative in January 2025 targeting protocol feasibility and site ranking, and early deployments in neurology cut site-identification cycles from twelve weeks to under five [9]. Cost avoidance matters here: a single non-enrolling site typically burns USD 40,000–60,000 in activation spend before it is closed.


Restraints Impact Analysis

Restraint weightings reflect analyst assessment of drag on growth momentum. They are directional indicators of friction intensity, not subtractive inputs to the compound growth calculation.

Restraint ~% Drag on CAGR Geographic Relevance Impact Timeline
Patient recruitment shortfalls and site attrition ~-1.2% Global Long-term (≥4 yr)
Escalating per-patient trial costs ~-0.9% North America, Europe Medium-term (2–4 yr)
Data privacy and cross-border transfer restrictions ~-0.7% Europe, China Medium-term (2–4 yr)
Investigator and coordinator workforce shortage ~-0.6% North America Short-term (≤2 yr)
Protocol complexity and amendment burden ~-0.5% Global Long-term (≥4 yr)


Recruitment Shortfalls

Roughly 80% of studies miss their original enrollment timeline, and close to a fifth of activated sites never randomize a single participant [12]. Delay is expensive in a way that compounds: each month of slippage on a late-stage program costs sponsors an estimated USD 600,000 to USD 8 million in deferred revenue depending on indication. Underrepresentation compounds the problem, since the FDA's diversity action plan requirements now oblige sponsors to justify enrollment demographics before pivotal study initiation.

Cost Escalation and Protocol Complexity

Per-protocol endpoint counts have roughly doubled over fifteen years, and the average pivotal study now carries more than 260 procedures per participant [10]. Amendments follow inevitably — sponsors implement an average of 2.3 substantial amendments per Phase III protocol, each costing USD 141,000 to USD 535,000 to execute across an active site network. Simplification programs exist, but competitive pressure to collect exploratory biomarker data keeps pushing complexity upward.

Data Governance Friction

Cross-border movement of participant data has become a legal engineering problem. The EU General Data Protection Regulation, China's Personal Information Protection Law, and India's Digital Personal Data Protection Act each impose distinct localization and consent standards, forcing sponsors to maintain regional data enclaves [13]. Multi-region programs now budget six to nine additional weeks purely for data-transfer impact assessments.


Clinical Trials Market Opportunities

Decentralized Service Platforms

Remote visit orchestration, direct-to-participant logistics, and connected-device endpoint capture form the fastest-expanding service line in the Clinical Trials Market at 13.58% CAGR. Vendors that bundle these into a single contracted offering — rather than selling point tools — capture premium margins because sponsors are consolidating vendor counts.

Asia-Pacific Enrollment Corridors

Chinese and Indian regulators now clear standard protocols in roughly 30 days, and per-participant costs run 40–55% below U.S. benchmarks [11]. Sponsors building dedicated Asia-Pacific site networks rather than opportunistic rescue enrollment are securing durable timeline advantages.

Rare-Disease and Adaptive Master Protocols

Basket and platform studies let a single infrastructure serve multiple investigational arms, cutting per-arm setup costs by an estimated 30%. With more than 7,000 rare conditions and fewer than 5% having approved therapies, adaptive master protocols represent the most capital-efficient route into small populations.

Trial Data Monetization and Secondary-Use Models

Sponsors and contract research organizations are commercializing de-identified operational and clinical datasets through synthetic control arms and external comparator services. Regulators accepted external controls in a growing share of oncology submissions, creating a licensing market for curated legacy study data that barely existed in 2020 [7].

Site Network Consolidation and Embedded Research

Integrated delivery networks are embedding research units inside routine care, converting standing patient panels into pre-qualified pools. This model addresses the enrollment gap directly and gives sponsors predictable throughput, which is why site-network operators attracted more than USD 2.1 billion in private capital between 2023 and 2025 [14].


Clinical Trials Market Future Outlook

Agentic Automation Across Study Operations

Trial operations will absorb autonomous software agents faster than most clinical functions because the work is rule-bound and document-heavy. Sponsors already pilot agents for query resolution, safety narrative drafting, and protocol deviation triage, with early deployments reporting 30–40% reductions in data-management hours [9]. By 2030, expect regulatory submissions where agent-generated content is disclosed as a matter of routine rather than exception.

Platform Economics in Contract Research

Consolidation reshapes vendor relationships. Large contract research organizations increasingly sell technology-plus-service bundles under multi-year strategic partnerships, and the top providers now derive a growing revenue share from software subscriptions rather than headcount pass-through. This shifts competitive advantage toward firms owning both the data layer and the delivery workforce.

Precision Medicine and Biomarker-Gated Enrollment

Genomic prescreening will become standard practice in oncology and neurology, shrinking eligible populations while raising response rates. Smaller, richer studies cost less in aggregate but demand far wider site networks to find qualifying participants, which is why sponsors are investing in registry partnerships and testing-reimbursement arrangements ahead of protocol finalization [6].

Sustainability and Trial Carbon Accounting

Environmental reporting has reached study design. Sponsors report that a single global Phase III program generates emissions comparable to several hundred transatlantic flights, driven largely by monitoring travel and comparator shipping. Hybrid execution cuts that footprint materially, and by 2030 sustainability metrics will appear alongside cost and timeline in vendor scorecards under EU corporate sustainability reporting obligations [17].


Clinical Trials Market Segmentation

By Phase

Phase distribution within the Clinical Trials Market reflects where capital concentrates rather than where activity counts are highest.

Segment Metric (2025) Primary Demand Driver
Phase I 22.6% share First-in-human oncology and cell therapy dose escalation
Phase II 6.32% CAGR (2026–2035) Biomarker-driven proof-of-concept validation
Phase III 51.2% share Pivotal registration program scale and duration
Phase IV USD 4.12 billion Post-marketing commitments and label expansion


Phase III retains dominance because pivotal programs run longest and enroll widest — a cardiovascular outcomes study can exceed 15,000 participants across 40 countries. Phase II grows fastest for a different reason: dose-optimization expectations under Project Optimus have converted what was once a single-arm signal-seeking exercise into a randomized comparison, effectively doubling mid-stage sample sizes in oncology.

By Study Design

Design choice increasingly determines cost structure across the Clinical Trials Market.

Segment Metric (2025) Primary Demand Driver
Interventional / Treatment Studies 67.2% share Regulatory requirement for randomized evidence
Observational Studies USD 20.61 billion Payer evidence needs and post-approval surveillance
Adaptive / Other Designs 7.63% CAGR (2026–2035) Seamless Phase II/III efficiency in rare disease


Interventional work remains the backbone because approval still rests on randomized controlled trials. Adaptive formats grow fastest by eliminating the gap between mid- and late-stage programs; sponsors running seamless designs report timeline savings of eight to fourteen months, which in a competitive indication is worth more than the added statistical complexity costs.

By Service Type

Service mix within the Clinical Trials Market is shifting toward centralized and remote delivery.

Segment Metric (2025) Primary Demand Driver
Protocol Design & Feasibility 12.4% share Complexity reduction and site selection accuracy
Site Identification & Patient Recruitment USD 14.97 billion Enrollment shortfall mitigation
Clinical Trial Monitoring 26.5% share Data integrity obligations under ICH E6(R3)
Data Management & Biostatistics 19.1% share Endpoint volume growth and submission readiness
Regulatory & Safety Reporting USD 12.28 billion Multi-jurisdiction pharmacovigilance requirements
Decentralized Services 13.58% CAGR (2026–2035) Remote visit orchestration and connected devices


Monitoring holds the largest share, though its composition is changing rapidly as risk-based approaches replace universal source data verification. Recruitment services command the second-largest spend and the highest urgency, since every sponsor interviewed cites enrollment as the top program risk.

By Therapeutic Area

Therapeutic concentration in the Clinical Trials Market follows pipeline economics closely.

Segment Metric (2025) Primary Demand Driver
Oncology 27.6% share Antibody-drug conjugate and bispecific pipeline density
Neurology / CNS 8.46% CAGR (2026–2035) Alzheimer's disease-modifying therapy programs
Infectious Disease USD 10.77 billion Pandemic preparedness and antimicrobial resistance
Cardiovascular 11.4% share Long-duration outcomes study requirements
Metabolic & Endocrine USD 9.00 billion Incretin-class obesity program expansion
Immunology 9.3% share Autoimmune biologic and biosimilar comparators
Others 12.0% share Ophthalmology, dermatology, and women's health


Oncology leads by a wide margin and shows no sign of ceding position. Neurology grows fastest on the back of amyloid- and tau-targeting programs whose lengthy follow-up periods and imaging-heavy endpoints make each study unusually expensive per participant.

By Sponsor Type

Sponsor composition in the Clinical Trials Market has stayed remarkably stable even as funding sources diversify.

Segment Metric (2025) Primary Demand Driver
Pharmaceutical & Biopharmaceutical Companies 63.2% share Commercial pipeline advancement
Medical Device Companies USD 11.86 billion EU MDR clinical evidence requirements
Government & Non-Profit 6.98% CAGR (2026–2035) Public health priorities and pandemic preparedness funding
Academic & Other 9.2% share Investigator-initiated and comparative effectiveness work


Commercial sponsors dominate because they fund the pivotal programs that consume most of the budget. Government and non-profit funding grows faster, however, driven by pandemic-preparedness allocations and by public payers commissioning comparative effectiveness studies that industry has little incentive to run.


Regional Market Share Analysis

Region Metric (2025) Primary Investment Themes
North America 45.8% share Oncology pivotal programs, decentralized infrastructure, site network roll-ups
Europe USD 20.69 billion CTIS harmonization, biosimilar comparators, academic consortia
Asia-Pacific 7.34% CAGR (2026–2035) Enrollment corridors, regulatory acceleration, domestic biotech scale-up
South America USD 3.87 billion Vaccine and infectious disease studies, ANVISA modernization
Middle East & Africa 3.6% share Genomics programs, sovereign health investment, TB and HIV research
Total USD 84.11 billion

Geographic concentration in the Clinical Trials Market remains high, though the gradient is flattening as sponsors chase enrollment velocity outside saturated Western centers. The table below discloses one metric per region.


North America

Country Share of Region Key Driver
US 87.4% NIH funding base and dense academic medical center network
Canada 8.9% Harmonized CTA pathway and provincial research tax credits
Mexico 3.7% COFEPRIS timeline reform and cost-competitive site economics


The United States remains the reference market because approval consequences originate there. NIH obligations of roughly USD 47 billion annually seed an investigator base no other geography matches, and the FDA's Real-World Evidence Program continues to widen acceptable evidence formats [3][7]. Cost pressure is real, though: U.S. per-participant expense in oncology now exceeds USD 89,000, which is precisely what pushes sponsors toward hybrid execution and offshore enrollment support.

Europe

Country Metric (2025) Key Driver
Germany USD 4.31 billion Comprehensive cancer center network and BfArM efficiency
UK 19.6% share of region MHRA international recognition route and NHS data assets
France 6.21% CAGR (2026–2035) ANSM fast-track and France 2030 health innovation funding
Italy 9.2% share of region AIFA reorganization and regional ethics committee consolidation
Spain USD 1.94 billion Fastest ethics approval timelines in Western Europe
Nordic Countries 6.8% share of region Population registries enabling long-horizon follow-up
Russia 3.1% share of region Domestic sponsor activity under import-substitution policy
Rest of Europe USD 1.72 billion Central European site cost advantage


European momentum is regulatory rather than commercial. CTIS created a single front door, and the Accelerating Clinical Trials in the EU initiative set explicit targets for multinational study starts [1]. Germany's Medical Research Act, passed in 2024, introduced a standardized contract template that removed one of the most persistent site-activation bottlenecks. The UK, operating outside CTIS, has countered with a recognition procedure that leans on approvals from trusted regulators.

Asia-Pacific

Country Metric (2025) Key Driver
China 34.8% share of region NMPA 60-working-day implicit approval and domestic oncology pipeline
India 8.12% CAGR (2026–2035) CDSCO waiver provisions and large treatment-naive populations
Japan USD 3.44 billion PMDA consultation framework and aging-population indications
South Korea 11.2% share of region Concentrated tertiary hospital enrollment capacity
ASEAN USD 1.51 billion Singapore and Malaysia regional hub development
Rest of Asia-Pacific 5.4% share of region Australian R&D tax incentive for early-phase work


Speed is the regional currency. China's implicit-approval mechanism gave sponsors predictability that had been missing, and domestic biotechs now originate a substantial share of global oncology assets, licensing them outward with Chinese study data attached [11]. India's 2019 New Drugs and Clinical Trials Rules, amended repeatedly since, permit waivers for locally manufactured drugs already approved elsewhere. Australia continues to punch above its weight in first-in-human work because its 43.5% refundable R&D offset materially changes early-phase cash flow.

South America

Country Metric (2025) Key Driver
Brazil USD 2.29 billion Law 14.874/2024 establishing a national research framework
Argentina 17.4% share of region Strong investigator base in cardiology and endocrinology
Rest of South America 6.98% CAGR (2026–2035) Chilean and Colombian oncology site expansion


Brazil's 2024 clinical research law replaced a fragmented ethics apparatus with defined review deadlines, addressing the delay that had steered sponsors elsewhere for a decade. ANVISA has since committed to 90-day dossier assessment for priority indications. Regional strength concentrates in vaccine work and cardiometabolic studies, where large treatment-naive populations and centralized public hospital systems deliver enrollment rates roughly 1.8 times the North American average [15].

Middle East & Africa

Country Metric (2025) Key Driver
Saudi Arabia 31.6% share of region Vision 2030 health sector transformation and genomics program
UAE USD 0.61 billion Abu Dhabi biobank and expedited licensing framework
South Africa 22.4% share of region Established infectious disease and HIV research infrastructure
Egypt 7.28% CAGR (2026–2035) Hepatitis and oncology program scale-up
Rest of MEA USD 0.42 billion Pan-African regulatory harmonization under AMA


Sovereign investment drives activity here more than commercial sponsor demand. Saudi Arabia's Health Sector Transformation Program allocated significant capital to research infrastructure, and the Saudi Human Genome Program supplies population data of genuine scientific value. South Africa retains the continent's deepest investigator bench, built over three decades of HIV and tuberculosis research, and the African Medicines Agency is gradually assembling a continental review pathway [16].


Clinical Trials Market By Region, 2025-2035

Competitive Benchmarking

The concentration is in the medium range. The estimated Herfindahl-Hirschman Index for outsourced clinical development is 700-900; the top five providers have approximately 42-48 percent of contracted cost. The long tail is big: thousands of specialist and regional providers provide single-country programs and therapeutic niches. Differentiation in Clinical Trials: The market has now shifted to proprietary data assets and technical depth, not personnel scale. That’s why software-native newcomers have made inroads against traditional service organizations.

Company Est. Revenue Share Range Key Offerings for Clinical Trials Market Strategic Positioning
IQVIA Holdings ~13–16% Full-service development, Connected Intelligence platform, real-world data Data-and-analytics moat; broadest information asset base
ICON plc ~9–12% Global Phase I–IV delivery, laboratory services, decentralized solutions Scale integrator post-PRA; strong biotech franchise
Thermo Fisher (PPD) ~8–11% Clinical development, central laboratory, bioanalytical services Vertically linked to manufacturing and supply
Fortrea ~4–6% Phase I–IV delivery, patient access, enabling services Focused pure-play following Labcorp separation
Parexel ~4–6% Regulatory consulting, late-phase, biotech-dedicated units Regulatory strategy depth for first-time filers
Syneos Health ~3–5% Integrated clinical and commercial development Development-to-launch continuity model
Medpace ~2–4% Full-service delivery for small and mid-size sponsors Therapeutic-expert-led operating model
Charles River Laboratories ~2–4% Preclinical to early clinical transition, safety assessment Upstream discovery-to-clinic bridge
WuXi Clinical ~2–3% China and global study execution, site management Asia-Pacific enrollment corridor specialist
Veeva Systems ~2–3% Vault clinical suite, EDC, CTMS, eTMF Software-native unified clinical data layer
Medidata (Dassault Systèmes) ~2–3% Rave EDC, synthetic control arms, sensor data capture Legacy data corpus enabling external comparators
Oracle Life Sciences ~1–3% Clinical one platform, safety and pharmacovigilance Enterprise infrastructure and safety systems


Recent News & Developments

  • European Medicines Agency (January 2025): CTIS became the mandatory submission channel for all EU interventional studies, closing the three-year transition and eliminating parallel national dossiers [1]
  • IQVIA and Nvidia (January 2025): Announced a collaboration to build agentic AI foundation models for clinical development, targeting feasibility assessment and site ranking workflows [9]
  • ICH (January 2025): Adopted ICH E6(R3) good clinical practice, formally endorsing risk-proportionate monitoring and fitness-for-purpose data governance [8]
  • U.S. FDA (September 2024): Finalized guidance on decentralized study conduct, clarifying remote consent, local laboratory use, and direct-to-participant shipment obligations [2]
  • German Federal Government (October 2024): Medical Research Act took effect, introducing standardized site contract templates and a centralized specialized ethics committee [1]
  • Brazil (May 2024): Law 14.874 established a national clinical research framework with defined ethics review deadlines and sponsor obligations for post-study drug supply [15]
  • Sanofi and Formation Bio (May 2024): Launched an AI-driven development partnership with OpenAI aimed at compressing protocol authoring and regulatory document generation cycles [18]
  • Labcorp (July 2023): Completed the spin-off of Fortrea as an independent publicly traded clinical development organization, creating a new top-tier pure-play competitor [19]


Clinical Trials Market Report Scope

Parameter Detail
Market Scope Global Clinical Trials Market covering phase, study design, service type, therapeutic area, sponsor type, and geography.
Study Period 2021–2035 (Historical 2021–2024; Base Year 2025; Forecast 2026–2035)
CAGR 6.05% (2026–2035)
Market Size Checkpoints USD 84.11 billion (2025); USD 89.25 billion (2026); USD 119.72 billion (2031); USD 151.43 billion (2035)
Fastest Growing Segments Decentralized services (13.58% CAGR); Neurology (8.46% CAGR); Adaptive designs (7.63% CAGR); Asia-Pacific (7.34% CAGR)
Companies Profiled IQVIA, ICON plc, Thermo Fisher (PPD), Fortrea, Parexel, Syneos Health, Medpace, Charles River Laboratories, WuXi Clinical, Veeva Systems, Medidata, Oracle Life Sciences
Valuation Currency USD billion, constant 2025 dollars

FAQs

How should a mid-size biotech structure vendor contracts when entering the Clinical Trials Market for the first time?
Negotiate unit-based pricing with defined change-order thresholds rather than full-time-equivalent models, which expose small sponsors to scope drift. Cap pass-through costs at 25% of the direct services value [10].
What insurance and indemnification exposures apply to sponsors operating in the Clinical Trials Market?
Sponsors need per-study clinical trial liability coverage sized to jurisdictional minimums, which vary sharply — India and Brazil mandate compensation formulas that several European states do not [15]. Budget 0.5–1.2% of study cost.
When does a hybrid protocol cost more than a conventional site-based design?
Short-duration studies under nine months with fewer than 300 participants rarely recover the technology setup and logistics overhead. Break-even typically arrives around the 500-participant threshold [2].
How do buyers evaluate technology depth among Clinical Trials Market service providers?
Ask for verified cycle-time metrics on database lock, query rate per participant-visit, and site activation median — not platform demonstrations. Providers unwilling to share anonymized benchmarks usually lack them [9].
What regulatory nuance most often surprises sponsors expanding into Asia-Pacific?
Local ethics committees frequently require submission of country-specific informed consent translations validated by back-translation before national regulatory clearance, adding four to six weeks [11]. Sequencing these in parallel avoids the delay.
Are external control arms accepted as substitutes for concurrent randomization in the Clinical Trials Market?
Only in narrow circumstances — typically rare diseases with well-characterized natural history and objective endpoints. Regulators expect prospective agreement on the comparator dataset before enrollment begins [7].
What integration challenge derails technology deployments in the Clinical Trials Market most often?
Identity and access management across sponsor, site, and vendor systems. Coordinators managing eight or more separate logins per study show measurably higher data-entry error rates, which undermines any efficiency the platform promised [25].      
Author
Author
Author Profile
Vikita Thakur LinkedIn Senior Research Analyst
She holds an experience of about 5+ years in market research and business consulting projects for sectors such as life sciences, medical devices, and healthcare IT. She possesses a robust background in data analysis, market estimation, competitive intelligence, pipeline analysis market trend identification, and consumer behavior insights. Her expertise lies in technical Sales support, client interaction and project management, designing and implementing market research studies, conducting competitive analysis, and synthesizing complex data into actionable recommendations that drive business growth.
Co-Author
Co-Author Profile
Rahul Gotadki LinkedIn Research Manager
He holds an experience of about 9+ years in Market Research and Business Consulting, working under the spectrum of Life Sciences and Healthcare domains. Rahul conceptualizes and implements a scalable business strategy and provides strategic leadership to the clients. His expertise lies in market estimation, competitive intelligence, pipeline analysis, customer assessment, etc.

Research Approach


Secondary Research

The secondary research process involved comprehensive analysis of regulatory databases, clinical trial registries, peer-reviewed medical journals, therapeutic area publications, and authoritative health organizations. Key sources included the US Food & Drug Administration (FDA) ClinicalTrials.gov registry, European Medicines Agency (EMA) EU Clinical Trials Register, World Health Organization (WHO) International Clinical Trials Registry Platform (ICTRP), National Institutes of Health (NIH) protocol databases, National Center for Biotechnology Information (NCBI/PubMed), International Council for Harmonisation (ICH) guidelines, UK Medicines and Healthcare products Regulatory Agency (MHRA), Pharmaceuticals and Medical Devices Agency (PMDA) Japan, National Medical Products Administration (NMPA) China, CDC Division of HIV Prevention Clinical Studies, Centers for Medicare & Medicaid Services (CMS) clinical investigation databases, National Institute for Health and Care Research (NIHR) UK clinical trial portfolios, National Cancer Institute (NCI) Cancer Therapy Evaluation Program (CTEP), and national health ministry registries from key markets. These sources were used to collect trial enrollment statistics, regulatory submission data, protocol safety findings, therapeutic pipeline trends, and competitive landscape analysis for Phase I-IV trials across oncology, cardiology, neurology, infectious diseases, endocrinology, and other therapeutic areas.


Primary Research

Qualitative and quantitative insights were obtained by interviewing supply-side and demand-side stakeholders during the primary research process. CEOs, VPs of Clinical Operations, chief medical officers, regulatory affairs leaders, and business development directors from pharmaceutical companies, biotechnology firms, and contract research organizations (CROs) comprised supply-side sources. Principal investigators, clinical trial site coordinators, chief scientific officers from academic medical centers, research ethics board chairs, patient advocacy group leaders, and procurement heads from research hospitals, investigative sites, and clinical research units comprised demand-side sources. Market segmentation was validated across clinical phases, drug development pipeline timelines were confirmed, and insights were garnered on site activation patterns, patient recruitment strategies, decentralized trial adoption, and contracting fee structures through primary research.

Primary Respondent Breakdown:

By Designation: C-level Primaries (32%), Director Level (30%), Others (38%)

By Region: North America (38%), Europe (25%), Asia-Pacific (28%), Rest of World (9%)


Market Size Estimation

Global market valuation was derived through service revenue mapping and trial enrollment volume analysis. The methodology included:

Identification of over 45 critical clinical service providers in North America, Europe, Asia-Pacific, and Latin America

Service mapping across Phase I, Phase II, Phase III, and Phase IV trial categories including interventional, observational, and expanded access studies

Analysis of reported and modeled annual revenues specific to clinical trial service portfolios spanning protocol design, site management, patient recruitment, data management, and regulatory submission services

Coverage of CROs, pharmaceutical sponsors, and biotechnology companies representing 70-75% of global market share in 2024

Extrapolation using bottom-up (enrollment volume × cost per patient by therapeutic area and phase) and top-down (service provider revenue validation) approaches to derive segment-specific valuations across oncology, neurology, cardiology, infectious diseases, and endocrinology trials

This methodology framework is specifically adapted for the Clinical Trials Market segments including Phase I-IV categorization, interventional and observational study designs, and therapeutic areas such as oncology, cardiology, and neurology as outlined in the report scope

Download Free Sample

Kindly complete the form below to receive a free sample of this Report

Download PDF ×

We do not share your information with anyone. However, we may send you emails based on your report interest from time to time. You may contact us at any time to opt-out.