Occupational Health Market (2026 - 2035)

Occupational Health Market Research Report By Service Type (Health Screening, Wellness Programs, Occupational Safety Training, Drug Testing, Telehealth Services), By Industry (Manufacturing, Construction, Healthcare, Transportation, Education), By End User (Small Enterprises, Medium Enterprises, Large Enterprises), By Geographic Scope (North America, Europe, Asia Pacific, Latin America, Middle East and Africa) and By Regional (North America, Europe, South America, Asia Pacific, Middle East and Africa) - Growth & Industry Forecast 2025 To 2035
ID: MRFR/HC/41434-HCR 200 Pages Rahul Gotadki, Vikita Thakur Last Updated: September 17, 2026
Occupational Health Market
Market Size
Forecast Period2026-2035
CAGR (2026-2035)6.24%
2025 Market SizeUSD 5.91 Billion
2035 Market SizeUSD 10.78 Billion
Key Players
Concentra Group Holdings
Sonic Healthcare
Optum
Marsh McLennan
Medcor
Wolters Kluwer
Opportunities
  • Predictive Analytics on Longitudinal Exposure Records
  • Virtual-First Coverage for Distributed and Gig Workforces
  • Emerging-Market Formalisation

Occupational Health Market Summary

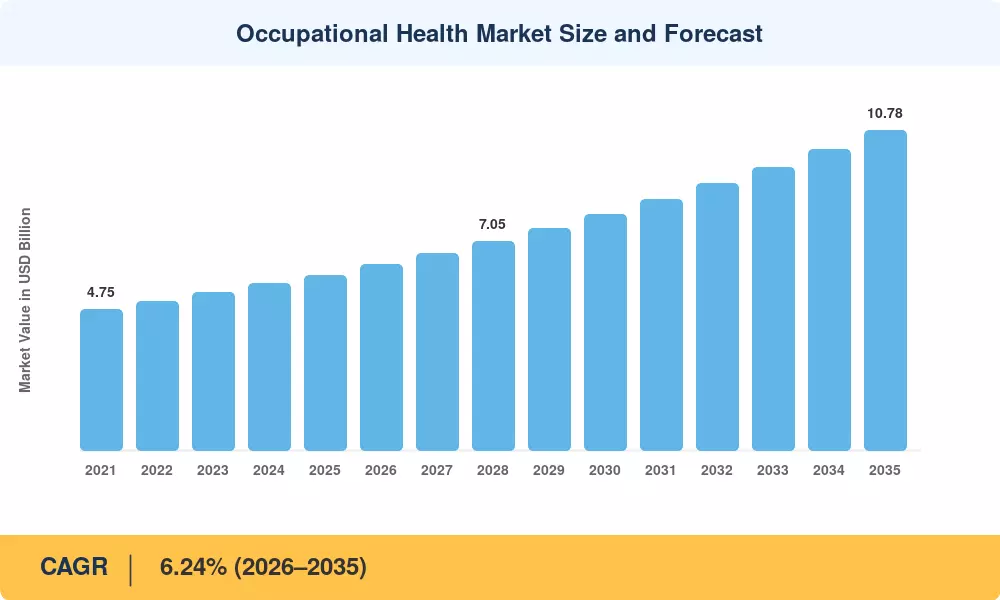
The Occupational Health Market reached USD 5.91 billion in 2025 and opens the forecast window at USD 6.25 billion in 2026, climbing to USD 10.78 billion by 2035 at a 6.24% CAGR. Two catalysts anchor that trajectory. First, the International Labour Organization's 2022 decision to elevate a safe and healthy working environment to a fundamental principle at work has pushed national labour inspectorates to tighten enforcement budgets and reporting requirements [1]. Second, the World Health Organization and ILO jointly attribute roughly 1.9 million annual deaths to occupational risk exposure, a figure that has reframed employer health spending from discretionary benefit to balance-sheet liability [2]. Employers are no longer buying isolated screening events; they are buying continuity of care.

Delivery models are being rebuilt underneath that demand. Paper-based fitness-for-duty files, standalone audiometry booths, and third-party medical records held in disconnected silos are giving way to integrated occupational health information systems that link exposure monitoring, case management, and return-to-work pathways in one record. Wearable dosimetry and computer-vision ergonomics assessment now feed the same platform that schedules clinician visits. The European Agency for Safety and Health at Work has built its 2023–2025 Healthy Workplaces Campaign around digitalisation of work, explicitly covering algorithmic management and remote-work health risk [3]. Spending on this software and analytics layer, though a minority of total revenue, is growing at roughly twice the pace of clinical service delivery.

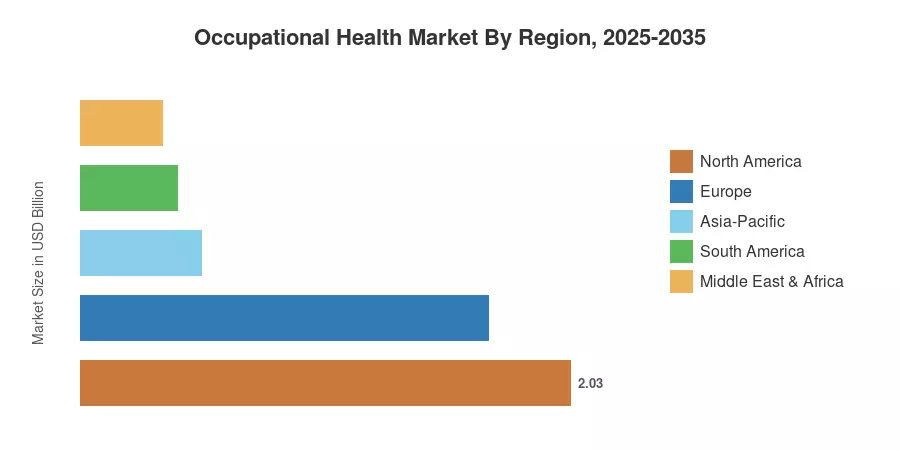
Regionally, North America holds 34.3% of the Occupational Health Market in 2025, sustained by OSHA recordkeeping obligations and employer-funded health infrastructure. Asia-Pacific expands fastest at an 8.47% CAGR through 2035 as manufacturing employment formalises across India, Vietnam, and Indonesia. Europe ranks second, where the revised Asbestos at Work Directive and psychosocial risk regulation keep compliance spending structurally elevated [4]. The next decade favours providers that can scale clinical capacity and data infrastructure simultaneously.


Key Report Takeaways

• By Service Type

  • Drug and alcohol testing held 34.3% of Occupational Health Market revenue in 2025, reflecting mandatory testing regimes in transport, mining, and energy.
  • Mental health services expand fastest at an 11.20% CAGR through 2035 as psychosocial risk assessment becomes a statutory duty in several jurisdictions.

• By Service Location

  • On-site clinics generated USD 2.36 billion in 2025, remaining the anchor delivery channel for large industrial employers.
  • Telehealth and virtual platforms grow at a 10.94% CAGR, extending coverage to distributed and small-employer workforces.


• By Application

  • Physical wellbeing applications accounted for 38.7% of the Occupational Health Market in 2025.

• By Region

  • North America commanded a 34.3% share of the Occupational Health Market in 2025.
  • Asia-Pacific posts the fastest regional growth at an 8.47% CAGR through 2035.
  • Middle East & Africa contributed USD 0.34 billion in 2025, led by Gulf industrial diversification programmes.


Market Size and Forecast (2021–2035)

Figures below combine employer health-spend disclosures from listed occupational health providers, national labour ministry inspection and compliance data, insurer claims aggregates, and a bottom-up build of covered-employee populations by organisation size band. Historical years reconcile against audited provider revenue; forecast years apply a demand model weighted by formal employment growth, regulatory intensity, and digital delivery penetration. All values are expressed in USD billion.
Occupational Health Market Size and Forecast
Our Impact

Enabled $4.3B Revenue Impact for Fortune 500 and Leading Multinationals

Partnering with 2000+ Global Organizations Each Year

30K+ Citations by Top-Tier Firms in the Industry

Driver Impact Analysis

Driver ~% Impact on CAGR Geographic Relevance Impact Timeline
Statutory tightening of exposure limits and inspection regimes +1.1 pp Global Medium-term (2–4 yr)
Rising musculoskeletal disorder prevalence and claim costs +0.9 pp North America, Europe Long-term (≥4 yr)
Psychosocial risk and mental health mandates +1.0 pp Europe, Asia-Pacific Medium-term (2–4 yr)
Telehealth and remote clinical delivery economics +0.8 pp Asia-Pacific, South America Short-term (≤2 yr)
Employer cost pressure from absenteeism and presenteeism +0.7 pp North America Short-term (≤2 yr)
Wearable and sensor-based continuous exposure monitoring +0.6 pp Global Long-term (≥4 yr)
Formalisation of employment in emerging economies +0.5 pp Asia-Pacific, Middle East & Africa Long-term (≥4 yr)


Regulatory Tightening on Hazardous Exposure

Europe reset the compliance baseline when Directive (EU) 2023/2668 cut the occupational exposure limit for asbestos to 0.01 fibres per cubic centimetre, a tenfold reduction with a transition path running to 2029 [4]. Member states must build surveillance registers for exposed workers, which converts a one-off remediation cost into a multi-year medical monitoring contract. Renovation-heavy economies feel this most: the European Commission estimates that a large share of the EU building stock predates asbestos bans, putting several million construction workers inside the surveillance perimeter. Providers with certified fibre-analysis laboratories and longitudinal record-keeping systems capture a disproportionate share of that spend.

Musculoskeletal Disorder Burden

In industrialized economies, ergonomic injuries continue to be the leading cause of missed workdays. Musculoskeletal complaints are among the most commonly reported work-related health issues in the EU, affecting the majority of workers who report any condition, according to data from national inspectorates and Eurostat [9]. In response, employers switched from post-injury physiotherapy referrals to predictive assessment, which uses camera-based motion capture to score lifting posture in real time and only triggers clinician evaluation over a risk threshold. Instead of compressing total addressable spend, that model increases the number of workers assessed while decreasing the cost per assessed worker.


Psychosocial Risk Becomes a Statutory Duty

In a number of jurisdictions, mental health transitioned from a voluntary benefit to an inspected duty between 2023 and 2025. Employers are legally required to evaluate stress risk under current legislation, as the UK Health and Safety Executive's Working Minds campaign makes clear, and inspectors now ask for proof of this evaluation during routine visits [6]. As a result, demand changed away from app-only services and toward manager training, clinician-led escalation procedures, and systematic psychosocial evaluations. This service line is expanding at the quickest rate in the occupational health market, with a CAGR of 11.20%.


Telehealth Economics for Distributed Workforces

Virtual delivery collapsed the cost floor for employers too small to justify an on-site clinic. A remote fitness-for-duty consultation can be delivered at a fraction of the fully loaded cost of a staffed clinic hour, and scheduling density improves clinician utilisation materially. EU-OSHA's 2023–2025 campaign on digital-age working conditions has legitimised remote occupational assessment within regulatory guidance, easing procurement resistance [3]. Micro-enterprises consequently grow at a 9.61% CAGR, well above the market average.


Restraints Impact Analysis

Restraint impacts are directional drag estimates reflecting the degree to which each constraint suppresses achievable growth. They are analyst-weighted, not additive, and should be interpreted as relative severity rankings.

Restraint ~% Impact on CAGR Geographic Relevance Impact Timeline
Shortage of accredited occupational medicine clinicians −0.7 pp Global Long-term (≥4 yr)
Fragmented cross-border regulatory requirements −0.6 pp Europe, Asia-Pacific Medium-term (2–4 yr)
Affordability barriers among small employers −0.6 pp Asia-Pacific, South America Medium-term (2–4 yr)
Health data privacy and consent constraints −0.5 pp Europe, North America Short-term (≤2 yr)
Difficulty quantifying programme return on investment −0.4 pp Global Short-term (≤2 yr)


Clinician Supply Is the Binding Constraint

Occupational medicine is a little specialty with a heavy workload. The specialty continuously ranks among the least-filled residency categories, and training pipelines in the US, UK, and Japan generate considerably fewer qualified experts each year than retirement attrition eliminates [12]. In response, providers assign scope to physician assistants and occupational health nurses in accordance with policy; nonetheless, a physician is still required for statutory sign-off for several certifications. Therefore, in a number of developed regions, the ceiling is set by capacity rather than demand.


Privacy Rules Complicate Data-Led Delivery

Continuous monitoring produces precisely the type of data that authorities are most concerned about protecting. Because of the inherent power imbalance in the job relationship, employee consent is viewed with suspicion under GDPR, which classifies health data as a separate category requiring an express legal justification [13]. For these reasons, wearable rollouts have been rejected by works councils in Germany and the Netherlands. Instead of using individual dashboards, vendors now build around aggregated, de-identified cohort statistics, which maintains compliance but undermines the therapeutic personalization that supported premium pricing.


Small Employer Affordability

Cost per covered worker rises steeply as headcount falls. A twelve-person workshop cannot amortise a retained clinician, and statutory minimums in many emerging economies apply only above employee thresholds, removing the compliance trigger entirely. Micro-enterprises therefore hold just 6.2% of 2025 demand despite employing a large share of the global workforce [8]. Subsidised regional schemes and pooled purchasing consortia are the realistic unlock.


Occupational Health Market Opportunities

Predictive Analytics on Longitudinal Exposure Records

No insurer can duplicate the databases that providers with ten years' worth of audiometry, spirometry, and biological monitoring results sit on. Carriers can more correctly price experience-rated workers' compensation by modeling claim probability from exposure history, and clinicians can license de-identified cohort standards as a recurring revenue line separate from clinical fees. This causes a significant upward change in the gross margin structure.


Virtual-First Coverage for Distributed and Gig Workforces

Employers of platforms, field service organizations, and remote-first businesses lack a physical location for a clinic. They are served at low marginal cost through a subscription model that combines scheduled virtual consultations, asynchronous triage, and a network of contracted physical venues for referrals. The targeted population grows annually as non-traditional employment increases, and telehealth's 10.94% CAGR indicates early traction.


Emerging-Market Formalisation

India's Occupational Safety, Health and Working Conditions Code consolidates thirteen prior statutes and extends coverage obligations to establishments previously outside the net [8]. Similar consolidation is underway across ASEAN. Providers that establish accredited local capacity ahead of enforcement capture first-mover share in markets where the Occupational Health Market is currently underpenetrated relative to industrial employment.

Integrated Return-to-Work Case Management

Absence duration, not incident frequency, drives employer cost. Bundling clinical treatment, insurer liaison, and graduated return-to-duty planning into a single accountable contract lets providers price on outcomes — days saved — rather than encounters delivered. Early outcome-based contracts in Nordic markets have demonstrated the model's viability at scale.

Heat and Climate-Related Health Programmes

Rising ambient temperatures are creating a service category that barely existed a decade ago. OSHA's proposed heat injury and illness prevention rule would require acclimatisation protocols, rest-break schedules, and monitoring for both outdoor and indoor work settings [7]. Gulf states already mandate midday work bans during summer months. Programme design, thermal monitoring, and worker training form a defensible new line.


Occupational Health Market Future Outlook

AI-Assisted Clinical Triage Relieves the Capacity Ceiling

Clinician scarcity forces automation of everything that does not require a licensed judgement. Algorithmic pre-screening of audiometry and spirometry results, automated flagging of abnormal biological monitoring values, and natural-language summarisation of occupational histories can compress physician review time per case substantially. Regulators are moving toward accommodation rather than prohibition, with medical device frameworks in both the EU and US now providing pathways for clinical decision support software. Providers that deploy these tools effectively convert the scarce specialist from a throughput bottleneck into an exception handler, and the Occupational Health Market's growth ceiling rises accordingly.

Platform Economics Reshape Provider Margins

Service delivery is a labour business; data is not. Vendors that own the system of record for exposure, absence, and case history can layer benchmarking, insurer analytics, and predictive risk products on a fixed cost base. Software and analytics revenue currently represents a minority of sector turnover but carries materially higher incremental margin than clinical hours. Expect consolidation as clinical networks acquire platform capability and platform vendors acquire clinical delivery to close the loop.

Outcome-Based Contracting Displaces Fee-for-Encounter

Buyers have grown sceptical of activity metrics. Contracts priced on lost-day reduction, claim frequency, or return-to-work duration transfer performance risk to the provider and reward genuine clinical effectiveness. Integrated Benefits Institute analysis consistently places the combined cost of absence and impaired productivity at a scale exceeding direct medical spend for many US employers, which gives procurement teams a credible denominator to contract against [10]. Providers lacking outcome measurement infrastructure will be excluded from these tenders.

Climate Adaptation Becomes a Permanent Service Category

Heat is now a structural occupational hazard rather than a seasonal inconvenience. The ILO has documented that a substantial share of the global workforce faces excessive heat exposure, with agriculture and construction most affected [14]. Regulatory responses are proliferating from the Gulf to the US Southwest. Thermal risk assessment, acclimatisation protocol design, and physiological monitoring will settle into the Occupational Health Market as a standing line item rather than a project engagement.


Regional Market Share Analysis

Region Metric (2025) Primary Investment Themes
North America 34.3% share OSHA compliance, workers' compensation cost control, on-site clinic networks
Europe 28.6% share Asbestos surveillance, psychosocial risk audit, cross-border harmonisation
Asia-Pacific 8.47% CAGR (2026–2035) Manufacturing formalisation, mobile screening units, telehealth scale
South America USD 0.40 Billion Mining and agribusiness medical surveillance
Middle East & Africa USD 0.34 Billion Heat-stress programmes, megaproject workforce health
Total USD 5.91 Billion —

The Occupational Health Market divides along regulatory intensity rather than economic size alone. Regions with codified employer duties and funded inspectorates convert industrial employment into service revenue at far higher rates than regions where obligations exist on paper only.


North America

Country Metric (2025) Key Driver
US 82.6% of regional share OSHA recordkeeping and workers' compensation experience rating
Canada USD 0.22 Billion Provincial WSIB return-to-work mandates
Mexico 7.14% CAGR (2026–2035) NOM-035 psychosocial risk standard enforcement


Employer economics dominate this region. Because US employers self-fund a large share of workers' compensation exposure, every avoided lost-time claim flows directly to operating income, which makes preventive spend an easy internal sale. Mexico's NOM-035 standard obliges employers to identify and analyse psychosocial risk factors, and inspection activity under it has broadened steadily since full-phase implementation. Canadian demand skews toward disability case management, reflecting provincial return-to-work obligations that place duration risk on the employer.

Europe

Country Metric (2025) Key Driver
Germany 24.8% of regional share Betriebsarzt statutory company physician requirement
UK USD 0.31 Billion HSE stress risk assessment duty
France 16.2% of regional share Services de prévention et de santé au travail reform
Italy USD 0.16 Billion Legislative Decree 81/2008 health surveillance
Spain 6.9% of regional share Construction sector asbestos remediation
Nordic Countries 7.31% CAGR (2026–2035) Outcome-based occupational health contracting
Russia USD 0.07 Billion Heavy industry mandatory periodic examinations
Rest of Europe 8.4% of regional share CEE manufacturing relocation


Germany's model is structurally distinctive: employers above defined thresholds must retain a company physician, creating a guaranteed demand floor insulated from economic cycles. France restructured its occupational health services under 2021 legislation to broaden the prevention mandate beyond medical examination toward workplace risk advisory, expanding the service perimeter per contract. The revised asbestos directive lands hardest on Spain, Italy, and Poland, where mid-century building stock and active renovation pipelines intersect [4].

Asia-Pacific

Country Metric (2025) Key Driver
China 31.6% of regional share Occupational disease prevention law enforcement in heavy industry
India 10.42% CAGR (2026–2035) OSH Code consolidation and factory inspection expansion
Japan USD 0.29 Billion Stress Check Programme statutory requirement
South Korea 11.7% of regional share Serious Accidents Punishment Act executive liability
ASEAN USD 0.17 Billion Electronics and garment supply-chain audit requirements
Rest of Asia-Pacific 6.8% of regional share Resource sector medical surveillance


South Korea created the sharpest incentive in the region: the Serious Accidents Punishment Act exposes senior executives to criminal liability for severe workplace incidents, which moved health and safety budgets from facility-level line items to board-level allocations. Japan's Stress Check Programme obliges larger employers to conduct annual psychological assessments, seeding a mature mental health service base. India represents the largest untapped pool — enormous industrial employment against limited accredited clinical capacity — and consequently posts the region's fastest country-level growth within the Occupational Health Market.

South America

Country Metric (2025) Key Driver
Brazil 61.3% of regional share eSocial digital reporting and PCMSO medical control programme
Argentina USD 0.06 Billion ART workers' compensation insurer requirements
Rest of South America 8.92% CAGR (2026–2035) Chilean and Peruvian mining health surveillance


Brazil digitised compliance ahead of most peers. The eSocial platform requires electronic submission of occupational health and safety events, which forced employers to formalise medical control programmes that previously existed only on paper, and providers with API-level integration into eSocial won share quickly. Andean mining operations sustain a separate premium niche around altitude physiology, silica exposure, and fitness-for-duty certification at remote sites.

Middle East & Africa

Country Metric (2025) Key Driver
Saudi Arabia 33.8% of regional share Vision 2030 megaproject workforce health mandates
UAE USD 0.08 Billion Midday work ban compliance and labour accommodation health
South Africa 19.4% of regional share Mine Health and Safety Act medical surveillance
Egypt 9.62% CAGR (2026–2035) Industrial zone expansion and labour law reform
Rest of MEA USD 0.05 Billion Oil and gas contractor health standards


Gulf construction created a concentrated, high-intensity demand pocket. Giga-project sites employ tens of thousands of workers in extreme heat, requiring on-site medical facilities, heat-stress monitoring, and accommodation-linked screening at a density unusual elsewhere. South Africa's mining sector operates one of the world's most prescriptive medical surveillance regimes, with statutory exit examinations and compensation-linked disease registers that generate steady annuity revenue.


Occupational Health Market By Region, 2025-2035

Occupational Health Market Segmentation

Segment structure in the Occupational Health Market reflects both what regulators require and what employers choose to buy voluntarily. Mandated services dominate current revenue; discretionary wellbeing services dominate growth.

By Service Type

Segment Metric (2025) Primary Demand Driver
Drug & Alcohol Testing 34.3% share Safety-sensitive role mandates in transport, mining, energy
Disease Screening USD 1.28 Billion Statutory periodic examination requirements
Health Risk Assessment 14.8% share Insurer premium differentiation
Injury Care & Case Management 7.05% CAGR (2026–2035) Workers' compensation duration control
Mental Health Services 11.20% CAGR (2026–2035) Psychosocial risk assessment duties
Vaccination & Immunisation USD 0.31 Billion Healthcare and food-processing sector requirements
Other Services 2.6% share Travel medicine, ergonomic consulting


Drug and alcohol testing retains scale because its demand is legally compelled rather than economically chosen. Federal transport regulations in the US, mine safety rules in Australia and South Africa, and offshore energy protocols worldwide all specify testing frequency, panel composition, and chain-of-custody procedure, which makes volumes largely insensitive to employer budget cycles. Margin pressure exists — laboratory testing has commoditised — so providers differentiate on collection-site density and turnaround time. Mental health services occupy the opposite position: growth is rapid, pricing is favourable, and delivery models remain unsettled, with employers still discriminating between clinically supervised programmes and thinly staffed digital apps.

By Service Location

Segment Metric (2025) Primary Demand Driver
On-Site Clinics USD 2.36 Billion Large-site manufacturing and logistics workforces
Off-Site / Third-Party Clinics 24.6% share Flexible capacity for mid-sized employers
Near-Site Shared Clinics 15.3% share Industrial park and business district clustering
Telehealth / Virtual Platforms 10.94% CAGR (2026–2035) Distributed workforce coverage economics
Mobile Units 7.8% share Remote site and multi-location screening campaigns


On-site clinics dominate the Occupational Health Market by revenue because proximity eliminates the productivity loss of off-site travel, which for a large plant outweighs the fixed cost of staffing. Shared near-site models are the interesting middle ground: several mid-sized employers in one industrial park jointly fund a facility none could justify alone, achieving on-site economics at off-site cost. Telehealth is not replacing physical delivery so much as extending the front door, handling triage and follow-up while reserving physical capacity for procedures that genuinely require presence.

By Application

Segment Metric (2025) Primary Demand Driver
Physical Wellbeing 38.7% share Musculoskeletal and chronic disease burden
Social & Mental Wellbeing 9.82% CAGR (2026–2035) Statutory psychosocial risk duties
Occupational Safety & Ergonomic Wellbeing USD 1.27 Billion Injury reduction and ergonomic redesign
Financial Wellbeing 12.4% share Retention and stress-reduction programmes


Physical wellbeing anchors the Occupational Health Market because it maps directly onto measurable claim costs. Employers can trace hypertension screening or ergonomic intervention to a specific reduction in absence days, which survives finance-team scrutiny. Social and mental wellbeing grows faster but faces a harder measurement problem, and buyers increasingly demand validated instruments rather than engagement metrics before renewing.

By Organisation Size

Segment Metric (2025) Primary Demand Driver
Large (250–4,999 employees) 46.1% share Statutory thresholds and dedicated HR infrastructure
Very Large (≥5,000 employees) USD 1.61 Billion Multi-site programme standardisation
Small (10–249 employees) 20.4% share Insurer and supply-chain audit requirements
Micro (<10 employees) 9.61% CAGR (2026–2035) Low-cost digital delivery removing affordability barrier


Large enterprises hold the plurality of the Occupational Health Market because most statutory obligations attach above employee thresholds these firms comfortably exceed, and because they possess the HR capacity to administer complex programmes. Micro-enterprises grow fastest from a small base, driven almost entirely by subscription telehealth products priced per employee per month. Supply-chain pressure matters here too: multinational buyers increasingly require tier-two suppliers to demonstrate worker health provision, pulling small firms into compliance without direct regulation.


Competitive Benchmarking

Concentration is moderate and geographically uneven. Estimated top-five combined share sits near 28–32% globally, with a corresponding HHI in the low hundreds — characteristic of a fragmented sector where national clinical networks, software vendors, and insurer-affiliated providers compete from different starting positions. No player holds a double-digit global share. Consolidation is accelerating as clinical networks acquire data platforms and vice versa, but regulatory licensing requirements keep local incumbents defensible in most jurisdictions.

Company Est. Revenue Share Range Key Offerings for Occupational Health Market Strategic Positioning
Concentra Group Holdings ~7–9% Occupational medicine centres, on-site employer clinics, injury care Largest US clinical network; scale advantage in workers' compensation
Sonic Healthcare (Sonic Healthcare Plus) ~5–7% Health surveillance, pre-employment screening, laboratory diagnostics Pathology-integrated model across Australia, UK, Germany
Optum (UnitedHealth Group) ~4–6% Employer clinics, behavioural health, population health analytics Payer-integrated; strongest data and risk-modelling assets
Marsh McLennan (Mercer Marsh Benefits) ~3–5% Health risk consulting, programme design, benefits integration Advisory-led entry point into employer health budgets
Medcor ~3–4% On-site and near-site clinics, injury triage, telehealth triage Triage-first model with strong construction and logistics penetration
Wolters Kluwer (Enablon) ~2–3% EHS software, incident management, exposure recordkeeping Enterprise software incumbent in heavy industry
Cority Software ~2–3% Occupational health information systems, industrial hygiene modules Purpose-built OHIS platform; deep clinical workflow coverage
VelocityEHS ~2–3% Ergonomics assessment, chemical management, health analytics AI-assisted ergonomics differentiation
Medigold Health ~1–2% Health surveillance, absence management, wellbeing services UK mid-market specialist with national clinician network
Axiom Medical ~1–2% Injury case management, behavioural health, return-to-work Outsourced case management focus for US employers
Examinetics ~1–2% Mobile audiometric and respiratory screening Mobile-unit specialist serving multi-site industrial clients


Recent News & Developments

  • OSHA (August 2024): Published a proposed rule on heat injury and illness prevention covering both indoor and outdoor work settings, which would establish acclimatisation, monitoring, and rest-break obligations for a broad employer population [7].
  • European Union (December 2023): Directive (EU) 2023/2668 entered into force, cutting the occupational asbestos exposure limit tenfold and mandating registers of exposed workers, triggering a multi-year surveillance procurement cycle across member states [4].
  • Concentra Group Holdings (July 2024): Completed an initial public offering on the New York Stock Exchange, separating from Select Medical and giving the sector its largest pure-play listed occupational medicine operator [15].
  • EU-OSHA (October 2023): Launched the Healthy Workplaces Campaign 2023–2025 on safe and healthy work in the digital age, covering algorithmic management, remote work, and worker-monitoring technologies [3].
  • UK Health and Safety Executive (2023–2024): Expanded the Working Minds campaign with sector-specific inspection guidance, reinforcing that stress risk assessment is a legal duty rather than a voluntary practice [6].
  • India, Ministry of Labour and Employment (2023–2025): Continued phased operationalisation of the Occupational Safety, Health and Working Conditions Code, consolidating thirteen prior statutes and extending coverage to previously exempt establishments [8].
  • Sonic Healthcare (2024): Extended its European laboratory and clinical services footprint through acquisition, strengthening the diagnostics base that underpins its health surveillance offering [16].
  • ILO (April 2024): Published analysis quantifying the scale of workforce exposure to excessive heat and related occupational hazards, elevating climate adaptation within national safety agendas [14].


Occupational Health Market Report Scope

Parameter Detail
Market Scope Global Occupational Health Market covering clinical services, screening and surveillance, case management, mental health services, and supporting software across all employer sizes and industry verticals
Study Period 2021–2035 (Historical 2021–2024; Base Year 2025; Forecast 2026–2035)
CAGR 6.24% (2026–2035)
Market Size Checkpoints USD 5.91 Billion (2025); USD 6.25 Billion (2026); USD 10.78 Billion (2035)
Fastest Growing Segments Mental Health Services (service type); Telehealth/Virtual Platforms (location); Micro Enterprises (organisation size); Asia-Pacific (geography)
Companies Profiled 11 major players including Concentra Group Holdings, Sonic Healthcare, Optum, Marsh McLennan, Medcor, Wolters Kluwer, Cority Software, VelocityEHS, Medigold Health, Axiom Medical, Examinetics
Valuation Currency USD Billion, constant 2025 prices

FAQs

How should procurement teams structure a tender for Occupational Health Market services?
Score bidders on clinician-to-worker ratios, average appointment lead time, and integration with existing HR systems. Require outcome commitments on absence duration rather than encounter volume. Insist on named clinical leadership rather than generic account management [10].
What integration challenges arise when replacing legacy occupational health record systems?
Historical exposure records often exist in non-standard formats with inconsistent worker identifiers, making migration the dominant cost. Statutory retention periods for exposure data can extend forty years, so legacy archives cannot simply be discarded [4].
Is the Occupational Health Market attractive for private equity investment?
Recurring contract revenue, regulatory demand floors, and a fragmented provider base support buy-and-build strategies. Clinician recruitment difficulty is the primary limit on organic scaling [12].
How do employers verify that a mental health vendor is clinically credible?
Ask for licensed clinician headcount, escalation protocols for acute risk, and validated outcome instruments rather than engagement statistics. Confirm professional indemnity coverage and local licensure in every operating jurisdiction [6].
Which Occupational Health Market services can realistically be delivered virtually?
Triage, mental health consultation, case management, and health risk assessment translate well to virtual delivery. Audiometry, spirometry, vision testing, and specimen collection require physical presence [3].
What distinguishes near-site shared clinics from traditional off-site providers?
Shared clinics are jointly funded by a defined employer group, giving members guaranteed capacity and dedicated staffing at a shared fixed cost. Off-site providers sell open-market capacity without any reserved allocation [5].
How does occupational injury prevention spending affect insurance pricing?
Experience-rated workers' compensation premiums respond to claim frequency and severity over a multi-year lookback. Documented preventive programmes can also qualify employers for insurer credits in several jurisdictions [19].      
Author
Author Author Profile Rahul Gotadki LinkedIn Research Manager
He holds an experience of about 9+ years in Market Research and Business Consulting, working under the spectrum of Life Sciences and Healthcare domains. Rahul conceptualizes and implements a scalable business strategy and provides strategic leadership to the clients. His expertise lies in market estimation, competitive intelligence, pipeline analysis, customer assessment, etc.
Co-Author Co-Author Profile Vikita Thakur LinkedIn Senior Research Analyst
She holds an experience of about 5+ years in market research and business consulting projects for sectors such as life sciences, medical devices, and healthcare IT. She possesses a robust background in data analysis, market estimation, competitive intelligence, pipeline analysis market trend identification, and consumer behavior insights. Her expertise lies in technical Sales support, client interaction and project management, designing and implementing market research studies, conducting competitive analysis, and synthesizing complex data into actionable recommendations that drive business growth.

Research Approach


Secondary Research

The secondary research process involved comprehensive analysis of regulatory databases, peer-reviewed medical and occupational health journals, clinical publications, and authoritative health and labor organizations. Key sources included the US Occupational Safety and Health Administration (OSHA), National Institute for Occupational Safety and Health (NIOSH), Bureau of Labor Statistics (BLS), European Agency for Safety and Health at Work (EU-OSHA), International Labour Organization (ILO), World Health Organization (WHO) Occupational Health Programme, Centers for Disease Control and Prevention (CDC) Workplace Safety and Health, National Institutes of Health (NIH) PubMed, European Centre for Disease Prevention and Control (ECDC), UK Health and Safety Executive (HSE), Safe Work Australia, Japan Ministry of Health, Labour and Welfare (MHLW), Health Canada, Singapore Ministry of Manpower (MOM), India Ministry of Labour and Employment, Eurostat Labour Force Survey, US Department of Labor, National Safety Council (NSC), American College of Occupational and Environmental Medicine (ACOEM), and International Commission on Occupational Health (ICOH). These sources were used to collect workplace injury statistics, regulatory compliance data, occupational disease surveillance, industry safety standards, service adoption trends, and market landscape analysis for health screening, wellness programs, occupational safety training, drug testing, and telehealth services.


Primary Research

In order to gather both qualitative and quantitative insights, supply-side and demand-side stakeholders were interviewed during the primary research process. CEOs, VPs of Operations, heads of regulatory compliance, commercial directors from occupational health service providers, third-party administrators, and corporate wellness vendors were examples of supply-side suppliers. Chief medical officers, occupational health doctors, corporate safety directors, human resources benefits managers, and procurement heads from the manufacturing, construction, healthcare, transportation, and education sectors were examples of demand-side sources. In addition to gathering information on pricing strategies, technology adoption trends, and the mechanics of regulatory compliance, primary research validated market segmentation and service growth schedules.

Primary Respondent Breakdown:

By Designation: C-level Executives (32%), Director Level (30%), Others (38%)

By Region: North America (32%), Europe (30%), Asia-Pacific (28%), Rest of World (10%)


Market Size Estimation

Global market valuation was derived through revenue mapping and service volume analysis. The methodology included:

Identification of 50+ key service providers across North America, Europe, Asia-Pacific, and Latin America

Service mapping across health screening, wellness programs, occupational safety training, drug testing, and telehealth categories

Analysis of reported and modeled annual revenues specific to occupational health service portfolios

Coverage of providers representing 72-78% of global market share in 2024

Extrapolation using bottom-up (employee count × service penetration × ASP by country) and top-down (provider revenue validation) approaches to derive segment-specific valuations

Download Free Sample

Kindly complete the form below to receive a free sample of this Report

Download PDF ×

We do not share your information with anyone. However, we may send you emails based on your report interest from time to time. You may contact us at any time to opt-out.