Brain Computer Interface Market (2026 - 2035)

Brain Computer Interface Market Size, Share and Research Report By Component (Hardware, Software & Algorithm, and Services), By Interface (Motor BCI, Communication BCI, Sensory & Neurofeedback BCI, and Cognitive & Affective BCI), By Application (Neuro-Prosthetics & Motor Restoration, Communication & Assistive Technology, Neurological Disorder Management, Gaming & Entertainment, Smart Home & Environmental Control, and Others), By End User (Hospitals & Clinics, Research & Academic Institutes, Home Care Settings, and Others), And By Region (North America, Europe, Asia-Pacific, And Rest Of The World) – Industry Forecast Till 2035
ID: MRFR/ICT/6940-CR 200 Pages Apoorva Priyadarshi, Aarti Dhapte Last Updated: September 15, 2026
Brain Computer Interface Market
Market Size
Forecast Period2026-2035
CAGR (2026-2035)10.7%
2025 Market SizeUSD 1.34 Billion
2035 Market SizeUSD 3.70 Billion
Key Players
Medtronic plc
Natus Medical Incorporated
Nihon Kohden Corporation
Compumedics Limited
Brain Products GmbH
g.tec medical engineering GmbH
Opportunities
  • Speech Neuroprosthesis as a Distinct Clinical Category
  • Decoder Licensing and Recurring-Revenue Models
  • Emerging-Market Rehabilitation Programs

Brain Computer Interface Market Summary

The Brain Computer Interface Market closed 2025 at roughly USD 1.34 billion and opens the forecast window at USD 1.48 billion in 2026, climbing to USD 3.70 billion by 2035 at a 10.7% CAGR. Two catalysts anchor that trajectory. The U.S. BRAIN Initiative has committed more than USD 3.0 billion in cumulative federal neuroscience funding since inception, and the FDA's Breakthrough Devices Program has granted designation to over a dozen implanted and wearable neural interface systems, compressing review timelines that once stretched past seven years [1][4].

Clinical practice is shifting away from open-loop deep brain stimulators and single-purpose assistive switches toward closed-loop, adaptive neural systems that read cortical activity and adjust therapy in milliseconds. Machine-learning decoders now run on edge silicon inside the implant housing rather than on a tethered workstation. Horizon Europe has allocated approximately EUR 1.1 billion to brain health and neurotechnology calls across its 2021–2027 cycle, and private neurotech financing exceeded USD 900 million in 2024 alone [3][12]. That capital is rebuilding the electrode, the amplifier, and the algorithm simultaneously.

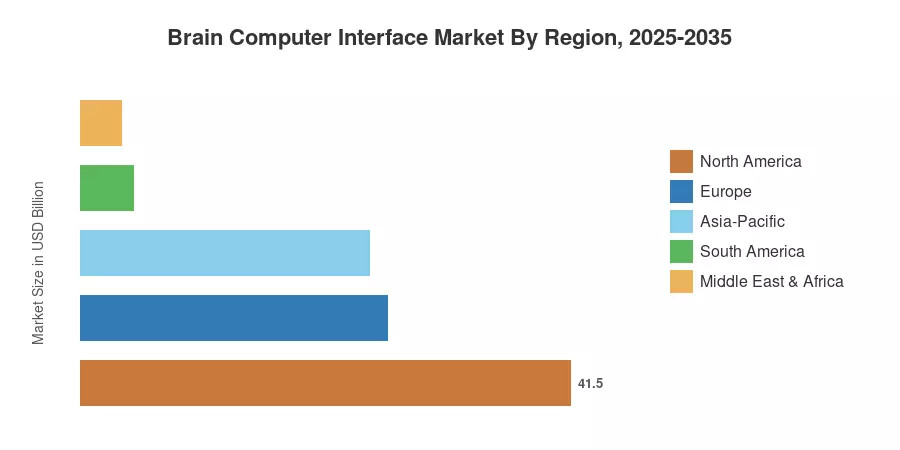
North America holds close to 41.5% of the Brain Computer Interface Market, supported by concentrated academic-clinical consortia and the deepest venture base. Asia-Pacific expands fastest at a 13.1% CAGR, driven by the China Brain Project and Japan's AMED neuro-rehabilitation portfolio. Europe follows at roughly 26.0%, where medical device regulation and neurorights debate are shaping product design as much as physiology does. The next decade will decide whether the Brain Computer Interface Market matures into reimbursed standard-of-care or remains a specialist frontier.


Key Report Takeaways

• By Technology

  • Hardware commands approximately 58.5% of the Brain Computer Interface Market in 2025, reflecting the cost weight of electrode arrays, amplifiers, and implantable housings
  • Software & Algorithm is the fastest-scaling component layer as decoding accuracy — not sensor count — becomes the competitive variable


• By Interface Type

  • Motor BCI leads the interface dimension with an 11.2% forecast CAGR through 2035

• By Sector

  • Neuro-Prosthetics & Motor Restoration accounted for roughly USD 0.42 billion in 2025, the largest application block


• By End-user

  • Hospitals & Clinics represent about 44.0% of end-user demand, though home-care deployment is the steepest growth curve
  • Gaming & Entertainment remains a volume-led, low-ASP segment that contributes scale rather than margin

• By Region

  • North America holds close to 41.5% share of the Brain Computer Interface Market
  • Asia-Pacific posts a 13.1% CAGR, the fastest of any region
  • Middle East & Africa contributes roughly USD 0.05 billion, small but policy-accelerated


Market Size and Forecast (2021–2035)

Figures below are built bottom-up from device shipment counts, clinical-site installed base, and disclosed research grants, then reconciled top-down against neurology device spending reported by public health systems and company segment filings. Historical years reflect actual revenue capture across the Brain Computer Interface Market; forecast years apply adoption curves calibrated to trial enrollment and regulatory clearance pipelines.
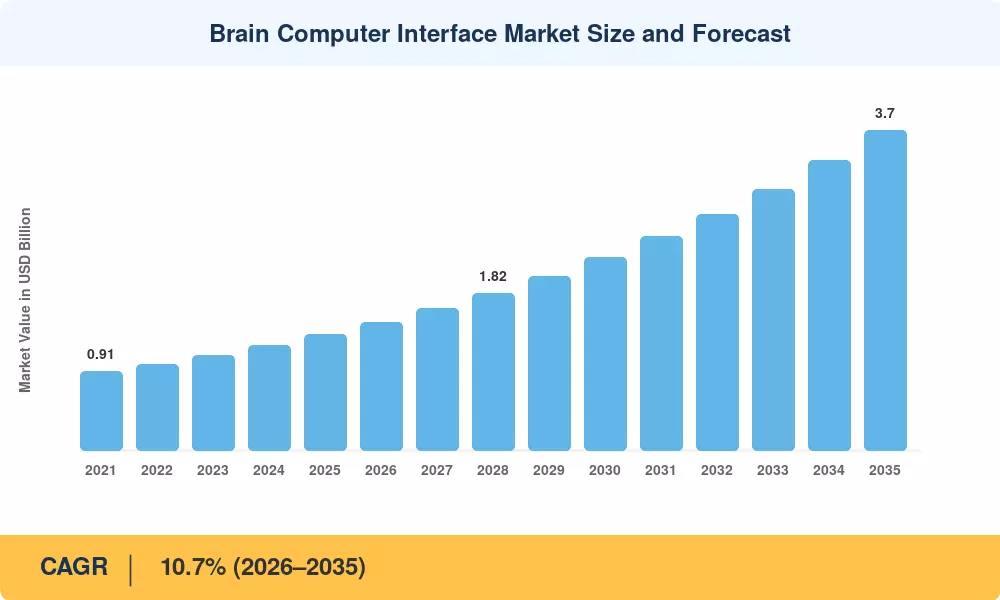
Brain Computer Interface Market Size and Forecast
Our Impact

Enabled $4.3B Revenue Impact for Fortune 500 and Leading Multinationals

Partnering with 2000+ Global Organizations Each Year

30K+ Citations by Top-Tier Firms in the Industry

Driver Impact Analysis

Driver ~% Impact on CAGR Geographic Relevance Impact Timeline
Rising stroke, ALS and spinal cord injury burden +2.1 Global Medium-term (2–4 yr)
Accelerated regulatory pathways for neural devices +1.8 North America, Europe Short-term (≤2 yr)
Sustained public neuroscience funding programs +1.7 Global Long-term (≥4 yr)
Machine-learning decoder and edge-compute advances +1.5 Global Medium-term (2–4 yr)
Venture and strategic capital inflows +1.3 North America, Europe Short-term (≤2 yr)
Ageing populations and assistive demand +1.2 Japan, Europe, North America Long-term (≥4 yr)
Dry-electrode and flexible thin-film sensor maturity +1.0 Asia-Pacific Medium-term (2–4 yr)


Neurological Disease Burden Converts Research Into Procurement

Twelve months after commencement, a significant portion of the approximately 15 million stroke victims worldwide still have upper-limb deficits [1]. The Brain Computer Interface Market is transformed from a laboratory curiosity to a rehabilitation line item by that demographic. In randomized crossover studies supported by NIDILRR funding totaling more than USD 25 million, non-invasive EEG-based brain-computer interfaces combined with robotic orthoses have demonstrated clinically significant Fugl-Meyer gains [7]. These systems are now compared to constraint-induced therapy on a cost-per-functional-point basis by rehabilitation directors.


Regulatory Machinery Is Catching Up With the Science

The FDA's 2021 implanted BCI leapfrog guidance provided sponsors with a specific non-clinical testing template, and its Breakthrough Devices Program significantly reduced the average time-to-decision for certified brain implants [4]. The first 510(k) clearance for a high-channel-count surface electrode was obtained by Precision Neuroscience in April 2025 for a thin-film cortical array that could be used for up to 30 days [15]. More than any trial abstract, clearance alters procurement psychology.


Public Programs Underwrite the Expensive Middle Years

Government money bridges the valley between proof-of-concept and reimbursed product. China's Brain Project committed multi-billion-yuan support across its 2021–2030 horizon, while Japan's AMED and Korea's MSIT fund neuro-rehabilitation consortia that guarantee early institutional demand [10][11]. Grant-funded installations at academic centres seed the clinical familiarity that later drives hospital capital budgets.

Decoding, Not Sensing, Now Sets the Ceiling

Electrode counts rose faster than usable bandwidth for most of the past decade. Transformer-based and state-space decoders changed that, lifting sustained communication rates in implanted speech-decoding trials past 60 words per minute against a prior ceiling near 18 [12]. Vendors that license decoder stacks are capturing recurring revenue where hardware vendors capture one-time revenue.


Restraints Impact Analysis

Restraint weightings are directional drag estimates reflecting the degree to which each barrier suppresses achievable adoption. They are analytical attributions, not subtractive CAGR components.

Restraint ~% Impact on CAGR Geographic Relevance Impact Timeline
Extended clinical validation timelines −1.9 Global Long-term (≥4 yr)
Chronic implant signal degradation and gliosis −1.5 Global Medium-term (2–4 yr)
Absence of dedicated reimbursement codes −1.3 North America, Europe Medium-term (2–4 yr)
Neural data privacy and neurorights legislation −0.9 Europe, South America Short-term (≤2 yr)
System cost and scarce trained clinical staff −1.1 Asia-Pacific, MEA, South America Long-term (≥4 yr)


Reimbursement Remains the Structural Bottleneck

What payers won't cover, hospitals won't scale. Sites are forced into unlisted codes with uncertain adjudication since there is currently no specific CPT Category I category for implanted BCI programming or decoder calibration [6]. Purchase decisions are pushed into research budgets that are an order of magnitude less than clinical capital budgets every quarter in the absence of a coding pathway, which limits realistic near-term volume across the Brain Computer Interface Market.


Chronic Recording Stability Still Undermines Long-Horizon Claims

As foreign-body response encapsulates recording sites after multi-year implantation, microelectrode arrays lose usable channels; by year three, several longitudinal cohorts show a significant yield loss [13]. Suppliers respond with subdural surface arrays and flexible polymer substrates that compromise durability for single-neuron resolution. The danger of revision surgery is a major consideration for buyers assessing a ten-year care route.


Neurorights Rules Are Arriving Before Product Standards

Chile amended its constitution to protect mental integrity, and Colorado and California extended data-privacy statutes to cover neural data in 2024 [17]. Ambiguity about what constitutes de-identified neural data complicates cloud-based decoder training and cross-border clinical collaboration. Compliance cost lands hardest on smaller entrants without regulatory affairs depth.


Brain Computer Interface Market Opportunities

Speech Neuroprosthesis as a Distinct Clinical Category

Implanted speech decoding has moved from single-subject demonstrations to multi-site trials, opening a category that competes with eye-tracking communication devices on both speed and dignity. Sites treating ALS and brainstem stroke represent an addressable base that existing assistive vendors already reach commercially.

Decoder Licensing and Recurring-Revenue Models

Algorithm vendors can monetize per-patient calibration subscriptions and continuous model updates rather than one-time hardware sales. Data monetization here is regulatory-sensitive but structurally attractive: federated training across hospital networks improves accuracy without moving raw neural signals, and the Brain Computer Interface Market rewards accuracy gains directly.

Emerging-Market Rehabilitation Programs

India's Ayushman Bharat infrastructure expansion and Brazil's SUS rehabilitation network create volume channels for lower-cost non-invasive systems that never require an operating theatre [18]. Local manufacturing partnerships can cut landed cost by a third and unlock tender eligibility.

Consumer Neurofeedback Bridging Into Clinical Validation

Wellness-grade headsets built consumer familiarity and drove electrode cost down. Vendors that convert that installed base into regulated indications — attention disorders, sleep staging, migraine management — capture margin expansion without rebuilding supply chains.

Surgical Robotics and Implantation Throughput

Automated insertion systems reduce theatre time and surgeon variability, which matters more than raw channel count once volumes exceed a few hundred procedures per year. Hospitals that can schedule implantation predictably will adopt earlier.


Brain Computer Interface Market Future Outlook

Adaptive, Closed-Loop Autonomy

Devices will increasingly decide when to stimulate rather than following fixed schedules. Adaptive deep brain stimulation approvals in 2025 established the regulatory template for algorithms that change therapy autonomously between clinic visits [16]. That precedent matters far beyond movement disorders.

Platform Economics Replace Device Economics

Value is migrating from the electrode to the decoder and the data pipeline. Vendors that own calibration software across multiple hardware form factors will capture disproportionate margin, mirroring how imaging software outgrew imaging hardware.

Reimbursement as the Inflection Variable

Establishment of dedicated procedure codes would do more for the Brain Computer Interface Market than any single technical advance. Coverage decisions in the United States and Germany typically cascade into other systems within three to five years [6].

Convergence With Rehabilitation Robotics and Wearables

Exoskeletons, functional electrical stimulation, and neural decoding are consolidating into single care pathways. WHO estimates over 2.5 billion people need assistive products, a demand pool that will pull the Brain Computer Interface Market toward integrated systems rather than standalone devices [9].


Regional Market Share Analysis

Region Share (2025) Primary Investment Themes
North America 41.5% Implant trials, decoder platforms, venture scale-up
Europe 26.0% MDR-compliant devices, neurorights governance, rehab robotics
Asia-Pacific 24.5% State neuroscience programs, dry-electrode manufacturing
South America 4.5% Public rehabilitation networks, neurorights leadership
Middle East & Africa 3.5% Sovereign health-tech funds, specialist centre buildout
Total 100.0% —

Regional distribution across the Brain Computer Interface Market reflects where clinical trial infrastructure, device regulation, and disposable health capital overlap.


North America

Country Metric Key Driver
US 84.0% share of region BRAIN Initiative and Breakthrough Device pipeline
Canada USD 0.06 Billion Provincial neuro-rehabilitation programs
Mexico 11.6% CAGR Private neurology centre expansion


Concentration in the United States is a function of institutional density: a handful of academic medical centres run most implanted trials, and their protocols become the de facto commercial specification. Canada contributes disproportionate algorithmic research relative to its device spend. The North American share of the Brain Computer Interface Market will erode gradually as Asia-Pacific volume compounds, though absolute dollars keep rising.

Europe

Country Metric Key Driver
Germany 23.5% share of region Clinical neurotechnology manufacturing base
UK USD 0.06 Billion NHS rehabilitation technology pilots
France 13.0% share of region National neuroscience research clusters
Italy 9.5% share of region Neuro-rehabilitation hospital network
Spain 7.5% share of region Assistive technology procurement programs
Nordic Countries 11.2% CAGR Digital health infrastructure maturity
Russia 4.0% share of region Domestic research institute demand
Rest of Europe USD 0.05 Billion Cross-border trial participation


European demand is shaped by the EU Medical Device Regulation, which raised clinical evidence thresholds and lengthened conformity assessment for Class III neural implants [5]. Germany's engineering base gives it a durable advantage in amplifier and electrode manufacture. Nordic health systems, with unified patient registries, offer the cleanest longitudinal outcome data any vendor can obtain.

Asia-Pacific

Country Metric Key Driver
China 34.0% share of region China Brain Project state funding
India 14.8% CAGR Rehabilitation infrastructure expansion
Japan 21.0% share of region AMED ageing-population neuro programs
South Korea USD 0.04 Billion MSIT neurotechnology roadmap
ASEAN 8.5% share of region Medical tourism specialist centres
Rest of Asia-Pacific 12.4% CAGR Academic research procurement


Growth leadership here rests on state direction rather than private capital. China's programme funds both invasive and wearable research tracks and has produced domestic implant trials that reduce import dependence [10]. Japan pairs demographic urgency with a mature rehabilitation reimbursement culture, making it the region's most commercially predictable market. India's contribution to the Brain Computer Interface Market will come from volume-priced non-invasive systems rather than implants.

South America

Country Metric Key Driver
Brazil 61.0% share of region SUS rehabilitation network procurement
Argentina USD 0.01 Billion University neuroscience programs
Rest of South America 11.9% CAGR Chile's neurorights framework and private clinics


Brazil anchors regional demand through public hospital rehabilitation budgets and a growing private neurology sector. Chile's constitutional neurorights amendment gave the region unexpected regulatory prominence, influencing draft legislation elsewhere [17]. Currency volatility remains the main brake on imported capital equipment.

Middle East & Africa

Country Metric Key Driver
Saudi Arabia 33.5% share of region Vision 2030 health sector transformation
UAE 26.0% share of region Specialist neuroscience centre investment
South Africa USD 0.007 Billion Academic hospital research capacity
Egypt 12.7% CAGR Public neurology service expansion
Rest of MEA 9.0% share of region Donor-funded rehabilitation programs


Sovereign health funds drive most procurement here, concentrating spend in flagship facilities rather than distributing it across systems. Saudi and Emirati centres import complete clinical programmes, including staff training contracts, which favours vendors offering managed service wrappers. Sub-Saharan adoption depends heavily on donor and academic partnership structures [18].


Brain Computer Interface Market By Region, 2025-2035

Brain Computer Interface Market Segmentation

Segmentation across the Brain Computer Interface Market follows component architecture, interface purpose, clinical application, and buyer type.

By Component

Segment Share (2025) Primary Demand Driver
Hardware 58.5% Electrode arrays, amplifiers, implant housings
Software & Algorithm 27.0% Decoder accuracy and calibration workflows
Services 14.5% Training, maintenance, clinical support


Hardware dominance reflects capital intensity, not strategic leverage. Within the Brain Computer Interface Market, software share expands steadily because decoder improvements can be shipped without new surgery. Services grow alongside installed base as hospitals demand uptime guarantees on devices that patients depend on daily.

By Interface

Segment CAGR (2026–2035) Primary Demand Driver
Motor BCI 11.2% Paralysis and stroke rehabilitation programs
Communication BCI 10.9% ALS and locked-in syndrome care
Sensory & Neurofeedback BCI 10.1% Attention, sleep and pain management
Cognitive & Affective BCI 9.8% Research, workload monitoring, gaming


Motor applications lead because functional restoration produces the clearest health-economic argument. Invasive BCI for paralysis rehabilitation delivers higher-fidelity control than any scalp-based alternative, but its growth is gated by surgical capacity rather than demand. Communication interfaces follow closely, benefiting from an existing assistive-device procurement channel across the Brain Computer Interface Market.

By Application

Segment Value (2025, USD B) Primary Demand Driver
Neuro-Prosthetics & Motor Restoration 0.42 Spinal cord injury and stroke caseload
Communication & Assistive Technology 0.29 Progressive neuromuscular disease
Neurological Disorder Management 0.26 Epilepsy and movement disorder therapy
Gaming & Entertainment 0.18 Consumer headset volumes
Smart Home & Environmental Control 0.11 Independent-living programs
Others 0.08 Defence, education, wellness research


Prosthetic and restoration use cases carry the deepest clinical evidence base, which is why they attract the largest share of trial funding within the Brain Computer Interface Market. Assistive communication converts faster commercially because it competes against an installed base of slower legacy devices with well-understood pricing.

By End User

Segment Share (2025) Primary Demand Driver
Hospitals & Clinics 44.0% Implantation, calibration, rehabilitation delivery
Research & Academic Institutes 33.5% Grant-funded experimental platforms
Home Care Settings 14.0% Remote decoder updates and telemonitoring
Others 8.5% Defence labs, wellness and gaming channels


Hospitals & Clinics represent the dominant end-use segment, accounting for 44.0% of the market. The segment's leading position is driven by the increasing adoption of advanced diagnostic, therapeutic, and rehabilitation technologies in clinical settings, supported by access to specialized infrastructure, sophisticated equipment, and trained healthcare professionals.

Research & Academic Institutes hold the second-largest share at 33.5%, supported by growing investments in neuroscience research, clinical trials, and the development and validation of innovative brain-computer interface technologies.

Home Care Settings account for 14.0% of the market, driven by the rising adoption of home-based rehabilitation, remote patient monitoring, and assistive technologies that enable patients to receive continued care outside traditional clinical environments. Other settings represent the remaining 8.5%, encompassing additional applications and care environments.


Competitive Benchmarking

Concentration sits in fragmented territory, with an estimated HHI near 780 and a top-five combined share of roughly 40%. Established neurodiagnostic manufacturers hold recurring EEG and monitoring revenue while venture-funded implant specialists hold the clinical narrative. That split creates persistent partnership and acquisition activity rather than head-to-head price competition.

Company Est. Revenue Share Range Key Offerings for Brain Computer Interface Market Strategic Positioning
Medtronic plc ~8–11% Adaptive DBS, neural sensing platforms Scale incumbent with reimbursement expertise
Natus Medical Incorporated ~6–8% EEG systems, neurodiagnostic software Installed-base leader in clinical monitoring
Nihon Kohden Corporation ~5–7% Clinical EEG, amplifier hardware Asia-Pacific clinical distribution strength
Compumedics Limited ~4–6% Research EEG, sleep and neuro platforms Research-channel specialist
Brain Products GmbH ~4–6% Research-grade amplifiers, analysis suites European academic standard-setter
g.tec medical engineering GmbH ~3–5% Rehabilitation BCI systems, decoder toolkits Clinical rehabilitation focus
Blackrock Neurotech ~3–5% High-channel implant arrays, research stacks Longest chronic human implant record
Cadwell Industries, Inc. ~3–4% Neurodiagnostic and monitoring systems Hospital procurement relationships
EMOTIV Inc. ~2–4% Wearable headsets, cloud analytics Consumer-to-enterprise crossover
NeuroSky, Inc. ~2–3% Single-channel sensor modules Component-level licensing model
Synchron Inc. ~1–3% Endovascular neural interface Least-invasive implant pathway
Neuralink Corporation ~1–3% High-bandwidth implant, robotic insertion Vertically integrated challenger
Precision Neuroscience ~1–2% Thin-film cortical surface arrays Cleared minimally invasive interface


Recent News & Developments

  • Neuralink (January 2024): Completed its first human implant under an investigational exemption, shifting investor and clinical attention toward high-channel implanted systems [14]
  • Synchron (2024): Reported one-year safety outcomes from its endovascular COMMAND trial, validating a vascular delivery route that avoids craniotomy [14]


  • Medtronic (February 2025): Received approval for adaptive, sensing-driven deep brain stimulation, establishing a closed-loop regulatory precedent [16]
  • Precision Neuroscience (April 2025): Obtained 510(k) clearance for a high-density thin-film cortical array for up to 30-day use [15]
  • China Brain Project (2025): Domestic invasive interface trials advanced under state programme funding, reducing reliance on imported hardware [10]
  • Onward Medical (2024): Expanded implanted stimulation trials combining spinal and cortical interfaces for upper-limb recovery [13]
  • U.S. FDA (2023–2025): Issued additional Breakthrough Device designations across implanted and wearable neural interface applicants [4]


Brain Computer Interface Market Report Scope

Parameter Detail
Market Scope Global Brain Computer Interface Market by component, interface, application, end user and geography
Study Period 2021–2035 (Historical 2021–2024; Base Year 2025; Forecast 2026–2035)
CAGR 10.7% (2026–2035)
Market Size Checkpoints USD 1.34 Billion (2025); USD 1.48 Billion (2026); USD 3.70 Billion (2035)
Fastest Growing Segments Motor BCI (interface); Software & Algorithm (component); Home Care Settings (end user)
Companies Profiled 13 global and regional participants
Valuation Currency USD (Billion), constant 2025 terms

FAQs

What procurement criteria matter most when hospitals evaluate suppliers in the Brain Computer Interface Market?
Uptime guarantees, calibration support hours, and revision-surgery liability terms outrank raw channel count. Buyers increasingly demand contractual decoder update commitments for the device's full service life [6].
How should investors think about hardware versus software exposure in the Brain Computer Interface Market?
Software carries higher gross margin and lower regulatory rework cost when models improve. Hardware exposure offers earlier revenue but ties capital to surgical volume growth [12].
Does endovascular delivery genuinely reduce clinical risk versus craniotomy?
It avoids opening the skull and uses established catheter workflows familiar to interventional teams. Signal resolution is lower, so it suits control and communication tasks rather than fine motor decoding [14].
What integration problems appear most often during deployment in the Brain Computer Interface Market?
Electrical interference from imaging suites and incompatible hospital EMR interfaces cause most delays. Sites underestimate the clinician training hours required before first patient use [18].
Are neural data privacy rules likely to restrict cloud-based decoder training?
Emerging statutes treat neural signals as sensitive personal data, complicating raw-signal transfer. Federated learning keeps data local and is becoming the default compliance architecture [17].
Which adjacent industries are entering this space?
Semiconductor firms supply low-power ASICs for on-implant processing, and rehabilitation robotics vendors bundle decoding into exoskeleton platforms. Both routes bypass building electrode capability from scratch [13].
What signals suggest a vendor is ready for commercial scale?
Multi-site trial enrollment, a cleared or approved indication, and a named reimbursement pathway together indicate readiness. Single-site demonstrations rarely translate into repeat hospital orders [19].    
Author
Author Author Profile Apoorva Priyadarshi LinkedIn Research Analyst
With 4+ years of experience in Market Intelligence and Strategic Research, Apoorv specializes in ICT, Semiconductor, and BFSI markets. Combining strong analytical capabilities with a deep understanding of technology-driven industries, he focuses on delivering data-driven insights that support strategic decision-making. With a background in technology and business research, Apoorv has contributed to numerous global market studies, competitive landscape analyses, and opportunity assessments across sectors such as semiconductors, digital banking, cybersecurity, and telecommunications.
Co-Author Co-Author Profile Aarti Dhapte LinkedIn AVP - Research
A consulting professional focused on helping businesses navigate complex markets through structured research and strategic insights. I partner with clients to solve high-impact business problems across market entry strategy, competitive intelligence, and opportunity assessment. Over the course of my experience, I have led and contributed to 100+ market research and consulting engagements, delivering insights across multiple industries and geographies, and supporting strategic decisions linked to $500M+ market opportunities. My core expertise lies in building robust market sizing, forecasting, and commercial models (top-down and bottom-up), alongside deep-dive competitive and industry analysis. I have played a key role in shaping go-to-market strategies, investment cases, and growth roadmaps, enabling clients to make confident, data-backed decisions in dynamic markets.

Research Approach


Secondary Research

The secondary research process involved comprehensive analysis of regulatory databases, peer-reviewed neurotechnology journals, clinical publications, and authoritative neurotechnology organizations. Key sources included the US Food & Drug Administration (FDA) Center for Devices and Radiological Health, European Medicines Agency (EMA), National Institutes of Health (NIH) BRAIN Initiative, Defense Advanced Research Projects Agency (DARPA) Biological Technologies Office, National Institute of Neurological Disorders and Stroke (NINDS), IEEE Engineering in Medicine and Biology Society, International BCI Society, Society for Neuroscience, PubMed Central/NCBI, European Commission Future and Emerging Technologies (FET) Programme, World Health Organization (WHO) Neurology and Neurosurgery Statistics, OECD Health Statistics, National Center for Health Statistics (NCHS), National Science Foundation (NSF) Neural Engineering reports, and neurotechnology regulatory databases from Health Canada, Japan's PMDA, and Australia's TGA. These sources were utilized to collect regulatory approval data (IDE/PMA pathways for implantable BCIs), clinical trial safety statistics, neuroprosthetics adoption metrics, neurological disorder demographics, defense neurotechnology contracts, and market landscape analysis for invasive BCI systems, non-invasive EEG headsets, semi-invasive electrocorticography devices, neural software platforms, and implantable neurostimulation technologies.


Primary Research

To gather both qualitative and quantitative insights, supply-side and demand-side stakeholders were interviewed during the primary research process. CEOs, VPs of Neural Engineering, heads of regulatory affairs, and commercial directors from companies that make brain-computer interfaces, neural hardware OEMs, and neurosoftware developers were examples of supply-side suppliers. Procurement leads from Veterans Affairs hospitals and military medical facilities, neurosurgeons and neurologists, physical medicine and rehabilitation specialists, neurotechnology researchers at academic medical centers, neurogaming developers, and assistive technology specialists at neurorehabilitation centers were all examples of demand-side sources. Primary research confirmed clinical trial timelines and regulatory pathways, validated market segmentation across invasive and non-invasive technologies, and collected data on defense neurotechnology procurement protocols, neural implant and software licensing pricing strategies, reimbursement dynamics for BCI-assisted rehabilitation, and clinical adoption patterns in neuroprosthetics.

Primary Respondent Breakdown:

By Designation: C-level Primaries (30%), Director Level (32%), Others (38%)

By Region: North America (40%), Europe (25%), Asia-Pacific (25%), Rest of World (10%)


Market Size Estimation

Global market valuation was derived through revenue mapping, implant volume analysis, and software licensing tracking. The methodology included:

Identification of 50+ key manufacturers across North America, Europe, Asia-Pacific (with specific focus on China and Japan), and emerging neurotechnology markets

Product mapping across invasive BCI (intracortical microelectrode arrays, electrocorticography systems), non-invasive BCI (EEG headsets, fMRI interfaces, NIRS systems), semi-invasive BCI (subcutaneous electrodes), neural signal processing software, and implantable pulse generator components

Analysis of reported and modeled annual revenues specific to neural hardware, neuroprosthetic devices, neurogaming software, and defense BCI systems

Coverage of manufacturers representing 75-80% of global market share in 2024

Extrapolation using bottom-up (procedure volume × ASP by country for implantable BCIs; unit shipments × licensing fees for neurosoftware; defense contract values) and top-down (manufacturer revenue validation, NIH/DARPA funding allocation analysis, neurotechnology VC investment tracking) approaches to derive segment-specific valuations

Download Free Sample

Kindly complete the form below to receive a free sample of this Report

Download PDF ×

We do not share your information with anyone. However, we may send you emails based on your report interest from time to time. You may contact us at any time to opt-out.