Atopic Dermatitis Market (2026 - 2035)

Atopic Dermatitis Market Research Report: Size, Share, Trend Analysis By Types (Chronic Atopic Dermatitis, Acute Atopic Dermatitis, Adult Atopic Dermatitis, Pediatric Atopic Dermatitis), By Treatment Type (Topical Corticosteroids, Topical Calcineurin Inhibitors, Biologics, Antihistamines), By Route of Administration (Topical, Systemic, Injectable), By Severity (Mild, Moderate, Severe) - Growth Outlook & Industry Forecast Till 2035

Forecast Period
2026-2035
CAGR
8.9%
2025 Market Size
USD 20.69 Billion
2035 Market Size
USD 48.53 Billion
Pharmaceutical ● Updated August 24, 2026 Report ID: MRFR/Pharma/1079-HCR | Pages: 200 | Author: Nidhi Mandole, Rahul Gotadki

Atopic Dermatitis Market Summary

The Atopic Dermatitis Market was valued at USD 20.69 billion in 2025 and enters the forecast window at USD 22.53 billion in 2026, climbing to USD 48.53 billion by 2035 at an 8.9% CAGR. Two catalysts anchor that trajectory. The US Inflation Reduction Act's Medicare Part D redesign capped annual out-of-pocket spending at USD 2,000 from January 2025, materially improving adherence economics for high-cost dermatology injectables [1]. In parallel, China's National Reimbursement Drug List added interleukin-targeted dermatology agents in its 2023 and 2024 cycles, collapsing a reimbursement lag that once ran four to five years [2].

The days of steroids-first sequencing when prescribing are well and truly gone. IL-4Rα, IL-13 and JAK-STAT modulators are substituting legacy regimens of topical corticosteroid therapy and short-course systemic immunosuppressants for sustainable control in moderate to severe illness. In 2024, Sanofi and Regeneron’s combined Dupixent worldwide net sales of over USD 14.1 billion reconfigured dermatology as a legitimate primary-care-adjacent sector [3].


North America represents 38.8% of global sales, driven by the extensive commercial coverage and dense expert networks. Asia-Pacific is the fastest-growing region at a CAGR of 10.2% through 2035. Europe is the second largest block on the strength of NICE and G-BA pathways that currently pass biologics within twelve months of EMA action [4]. The competitive advantage will move from novelty of molecules to convenience of dosing and depth of real-world evidence.


Key Report Takeaways

Segment-level economics inside the Atopic Dermatitis Market diverge sharply by therapeutic class and channel.

• By Drug Class

  • Corticosteroids retained 32.7% revenue share in 2025, still the volume backbone of first-line care.
  • Targeted biologics and JAK inhibitors are advancing at a 10.5% CAGR through 2035, the fastest class in the Atopic Dermatitis Market.
  • PDE-4 inhibitors contributed roughly USD 1.99 billion in 2025 revenue as non-steroidal maintenance gained traction

• By Sector

  • Topical formulations captured 57.5% of 2025 revenue across all care settings.
  • Injectables are expanding at a 9.9% CAGR, driven by extended dosing intervals.
  • Online pharmacies and tele-dermatology platforms are scaling at a 10.9% CAGR to 2035

• By Geography

  • North America commanded a 38.8% share of the Atopic Dermatitis Market in 2025
  • Asia-Pacific posts the fastest regional growth at 10.2% CAGR
  • Europe generated approximately USD 5.69 billion in 2025 revenue


Market Size and Forecast (2021–2035)

Estimates are based on national prescription audits, payer formulary disclosures, dermatology claims databases and reported net product sales by the twelve top manufacturers, triangulated with epidemiological prevalence models and corrected for gross-to-net erosion. Currency effects are adjusted to constant 2025 USD. Forecast figures for Atopic Dermatitis Market reflect approved-label growth, pediatric indication rollouts and observed biosimilar timing risk post-2032.
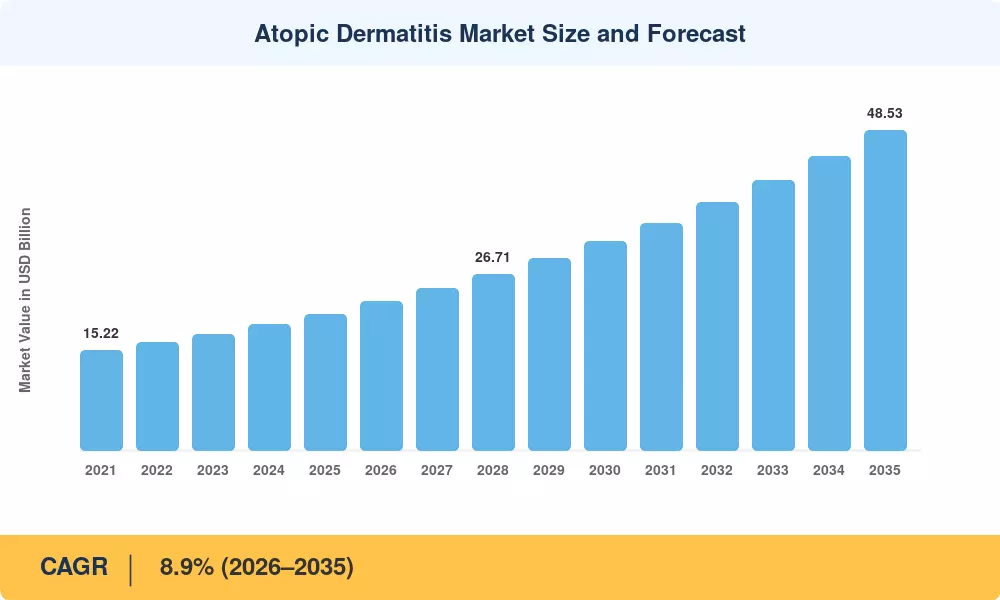
Atopic Dermatitis Market Size and Forecast
Our Impact
Enabled $4.3B Revenue Impact for Fortune 500 and Leading Multinationals
Partnering with 2000+ Global Organizations Each Year
30K+ Citations by Top-Tier Firms in the Industry

Driver Impact Analysis

Driver ~% Impact on CAGR Geographic Relevance Impact Timeline
Biologic and JAK label expansion into pediatrics 2.1 Global Medium-term (2–4 yr)
Payer reimbursement acceleration in Asia 1.7 Asia-Pacific Short-term (≤2 yr)
Rising diagnosed prevalence and disease awareness 1.4 Global Long-term (≥4 yr)
Tele-dermatology and AI triage reducing referral lag 1.1 North America, Europe Short-term (≤2 yr)
Out-of-pocket cost caps improving adherence. 0.9 North America Short-term (≤2 yr)
Non-steroidal topical innovation 0.8 Global Medium-term (2–4 yr)
Urbanization and environmental trigger burden 0.6 Asia-Pacific, MEA Long-term (≥4 yr)


Pediatric Label Expansion Rewrites Lifetime Value

Asian Reimbursement Timelines Collapsed

China's National Healthcare Security Administration negotiated dermatology biologics into the NRDL with price concessions averaging 55–62%, but paired those cuts with volume guarantees across roughly 1,400 tertiary hospitals [2]. Japan's Chuikyo maintained biologic listing within 90 days of PMDA approval, and Korea's HIRA extended coverage to moderate disease in 2024. The result is a compressed adoption curve: markets that once trailed the United States by half a decade now trail by eighteen months.

Digital Triage Shortens the Path to Specialists

Dermatology waiting lists remain the binding constraint in publicly funded systems. NHS England tracks substantial median waits for routine dermatology appointments, which are heavily constrained as two-week targets for suspected cancer pathways absorb primary clinical capacity. AI-assisted image triage is increasingly deployed across integrated delivery networks to help filter routine cases and optimize specialist slot allocation for moderate-to-severe patients.


Adherence Economics Improve With Cost Caps

Abandonment at the pharmacy counter has historically presented a major leak in dermatology treatment continuity. Policy mechanisms such as out-of-pocket spending caps and expanded manufacturer bridge programs directly target high patient cost-share thresholds, supporting improved long-term refill persistence and twelve-month continuation rates.


Restraints Impact Analysis

Restraint weightings reflect directional drag on the growth rate under base-case assumptions. They are analyst judgments informed by payer policy, safety surveillance, and pricing precedent — not additive subtractions from the forecast CAGR of the Atopic Dermatitis Market.

Restraint ~% Impact on CAGR Geographic Relevance Impact Timeline
Boxed warnings and JAK safety surveillance -1.3 Global Short-term (≤2 yr)
Step-therapy and prior-authorization friction -1.0 North America Medium-term (2–4 yr)
Price erosion from HTA reference pricing -0.8 Europe Long-term (≥4 yr)
Underdiagnosis in low- and middle-income settings -0.7 MEA, South America Long-term (≥4 yr)
Biosimilar entry post-2032 -0.6 Global Long-term (≥4 yr)


Safety Labeling Constrains Oral Systemic Uptake

The FDA's September 2021 class-wide boxed warning for JAK inhibitors—covering major adverse cardiovascular events, thrombosis, malignancy, and mortality—was extrapolated directly from the ORAL Surveillance rheumatoid arthritis trial rather than dermatology-specific data. Dermatologists nonetheless inherited the label, and clinical conservatism heavily restricts oral JAK therapy primarily to patients who have experienced biologic failures, capping a class that might otherwise experience faster adoption based on rapid itch relief.


Utilization Management Slows Conversion

Prior authorization remains a major administrative barrier to advanced systemic dermatology therapy. The American Medical Association's annual survey reports that physician practices process an average of 39 prior authorizations per physician per week, with 29% of physicians reporting that the process has led to a serious adverse event for a patient. Step-therapy protocols routinely mandate documented failures on conventional topicals or alternative therapies before biologic or targeted systemic approval, significantly extending the overall treatment pathway.


Diagnostic Capacity Limits Emerging Demand

Prevalence is not the constraint; diagnosis is. The World Health Organization's global health workforce data show dermatologist density below 0.1 per 100,000 population across much of sub-Saharan Africa, against 3.4 per 100,000 in the United States [17]. Without specialist throughput, generalists with steroid-only formularies manage severe disease, and the revenue never materializes regardless of underlying epidemiology.


Atopic Dermatitis Market Opportunities

OX40 and OX40L Pathway Commercialization

A third mechanistic class is arriving. Amgen and Kyowa Kirin's rocatinlimab and Sanofi's amlitelimab both target the OX40 axis, offering the prospect of drug-free remission intervals rather than continuous suppression — a proposition payers find structurally attractive. If Phase III durability holds, the class could capture 8–11% of the Atopic Dermatitis Market by 2033, drawing disproportionately from patients cycling between IL-13 agents.

Emerging-Market Volume Through Tiered Pricing

India's diagnosed patient pool exceeds 30 million, yet systemic therapy penetration sits in low single digits [9]. Manufacturers deploying tiered pricing with local fill-finish partnerships — the model AbbVie and Cipla piloted in immunology — can access volume without cannibalizing reference prices in Organisation for Economic Co-operation and Development markets.

Real-World Evidence as a Commercial Asset

Registry data has become a negotiating instrument. Manufacturers running longitudinal outcome registries enter reimbursement talks with persistence, hospitalization-avoidance and work-productivity evidence that HTA bodies increasingly demand. Monetizing that dataset through outcomes-based contracts represents a genuine business-model shift inside the Atopic Dermatitis Market.

Non-Steroidal Topicals for the Maintenance Gap

Roughly 60% of diagnosed patients have mild-to-moderate disease that never qualifies for systemic therapy. Topical JAK and aryl hydrocarbon receptor agonists address that gap with steroid-sparing profiles suitable for facial and intertriginous application, where corticosteroid atrophy risk has always limited use [12].

Direct-to-Patient Digital Channels

Tele-dermatology platforms bundling teleconsultation, prescription fulfillment and adherence coaching now capture a fifth of retail dermatology volume in the United States. Manufacturers integrating with these platforms gain first-fill visibility and a durable adherence lever.


Atopic Dermatitis Market Future Outlook

AI Moves From Triage to Treatment Selection

Image-based severity scoring is already regulated as software-as-a-medical-device in the EU under the MDR framework. The next step is predictive response modeling — algorithms that recommend IL-13 versus JAK versus OX40 based on biomarker and phenotype clusters. Manufacturers funding these tools gain influence over the switch decision, which is where most lifetime value in the Atopic Dermatitis Market is won or lost [11].

Dosing Convenience Becomes the Differentiator

Efficacy differences between leading biologics are narrowing toward clinical equivalence. Competition is migrating to administration burden: quarterly versus biweekly dosing, prefilled pen ergonomics for arthritic caregivers, and room-temperature stability for markets without reliable cold chain. Expect at least three quarterly-dosing approvals before 2030.

Outcomes-Based Contracting Scales

Payers in Germany, the Nordics and increasingly US integrated delivery networks are shifting risk onto manufacturers. Contracts tying rebate tiers to documented EASI-75 or ICH NRS-4 response require registry infrastructure that only the largest players can currently fund, which will consolidate share toward companies with mature evidence-generation capability [4].

Biosimilars Reshape the Back Half of the Decade

Key composition-of-matter protection on the leading IL-4Rα agent begins lapsing in major markets after 2031 [18]. Precedent from adalimumab suggests 30–45% price erosion within twenty-four months of multi-source entry, offset by volume expansion into previously unfunded moderate disease. Net effect on the Atopic Dermatitis Market is dilutive to revenue per patient but strongly accretive to treated population.


Atopic Dermatitis Market Segmentation

Segmentation of the Atopic Dermatitis Market follows drug class, route of administration, patient age group and distribution channel — the four axes that determine both pricing power and channel economics.

By Drug Class

Segment Metric (2025) Primary Demand Driver
Corticosteroids 32.7% share First-line protocol entrenchment
Biologics (IL-4/IL-13 inhibitors) 26.8% share Moderate-to-severe durable control
Topical Calcineurin Inhibitors USD 2.94 Billion Steroid-sparing facial application
JAK Inhibitors 10.5% CAGR (2026–2035) Rapid itch response
PDE-4 Inhibitors 9.6% share Pediatric maintenance safety profile
Emollients and Others USD 1.10 Billion Barrier repair adjunct use


Corticosteroids will remain the largest class by revenue into the early 2030s, but their share is eroding roughly 90 basis points annually as non-steroidal maintenance displaces long-term use. Biologics tell the opposite story. Growth within the Atopic Dermatitis Market is concentrated in the IL-4Rα and IL-13 classes, where a single patient generates annual net revenue between USD 18,000 and USD 32,000 depending on market and rebate structure. Persistence is the differentiator: twelve-month continuation for IL-13 agents exceeds 68%, against 41% for oral systemics constrained by monitoring requirements [7].

By Route of Administration

Segment Metric (2025) Primary Demand Driver
Topical 57.5% share Mild-to-moderate disease majority
Injectable 9.9% CAGR (2026–2035) Biologic class expansion
Oral USD 3.70 Billion Rapid onset in refractory cases


Topical dominance reflects epidemiology rather than value: most diagnosed patients never escalate. Injectables generate disproportionate revenue per unit and now account for roughly a quarter of the Atopic Dermatitis Market despite treating under 8% of the diagnosed population. Home administration removed the infusion-suite bottleneck entirely, which is why injectable growth outpaces oral despite the latter's convenience advantage.

By Patient Age Group

Segment Metric (2025) Primary Demand Driver
Adult (18+ yrs) 53.1% share Higher systemic therapy conversion
Pediatric (0–17 yrs) 9.3% CAGR (2026–2035) Infant and adolescent label expansion


Adults convert to high-value systemic therapy at roughly twice the pediatric rate, which is why they lead revenue despite comparable prevalence. The pediatric cohort is the strategic prize inside the Atopic Dermatitis Market — early initiation locks in decades of therapy. It may alter the atopic march toward asthma and allergic rhinitis, an argument manufacturers now deploy in HTA submissions [10].

By Distribution Channel

Segment Metric (2025) Primary Demand Driver
Retail Pharmacy 45.8% share Topical and oral prescription volume
Hospital Pharmacy USD 6.91 Billion Biologic initiation and specialist dispensing
Online / Tele-Dermatology 10.9% CAGR (2026–2035) Refill convenience and adherence programs


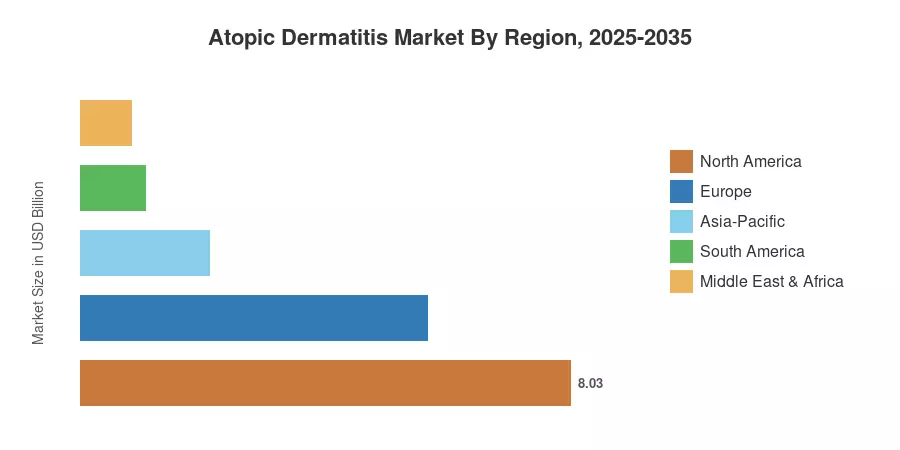
Regional Market Share Analysis

Region Metric (2025) Primary Investment Themes
North America 38.8% share Specialty pharmacy networks, outcomes contracting
Europe USD 5.69 Billion HTA dossier depth, biosimilar readiness
Asia-Pacific 10.2% CAGR (2026–2035) NRDL access, local manufacturing partnerships
South America USD 1.06 Billion Public tender participation, patient assistance
Middle East & Africa 4.0% share Specialist capacity building, private insurance
Total USD 20.69 Billion

Regional performance within the Atopic Dermatitis Market tracks payer sophistication more closely than disease prevalence, which is why Asia-Pacific's growth premium coexists with North American revenue dominance.


North America

Country Metric Key Driver
US 87.4% of regional revenue Commercial biologic coverage breadth
Canada USD 0.71 Billion pCPA joint negotiation efficiency
Mexico 9.4% CAGR (2026–2035) IMSS formulary expansion


Specialty pharmacy infrastructure explains why the United States converts prevalence into revenue more efficiently than any peer. Roughly 71% of biologic dermatology scripts route through limited-distribution networks that handle benefits investigation, copay assistance and injection training in one workflow [14]. Canada's pan-Canadian Pharmaceutical Alliance secured confidential rebates averaging 25–30% on dermatology biologics, trading price for faster provincial listing. Mexico's IMSS added interleukin inhibitors to its Cuadro Básico in 2024, opening a public channel that had previously been closed to the Atopic Dermatitis Market.

Europe

Country Metric Key Driver
Germany 24.1% of regional revenue AMNOG early benefit assessment speed
UK USD 0.86 Billion NICE technology appraisal throughput
France 15.8% of regional revenue ATU early-access pathway
Italy USD 0.53 Billion AIFA regional formulary alignment
Spain 8.7% of regional revenue Autonomous community tendering
Nordic Countries 9.1% CAGR (2026–2035) Registry-based outcomes contracting
Russia USD 0.24 Billion Domestic substitution policy
Rest of Europe 7.9% of regional revenue Central European access expansion


Germany's AMNOG process delivers reimbursed market access from day one of launch, with price negotiated retrospectively — a structural advantage no other large European system matches. NICE cleared multiple systemic dermatology agents through its technology appraisal route within 2023–2024, though managed access agreements attached severity thresholds using EASI-16 scoring [4]. Nordic payers have gone furthest on outcomes contracting, tying rebate tiers to registry-confirmed EASI-75 response at week 16.

Asia-Pacific

Country Metric Key Driver
China 34.6% of regional revenue NRDL listing and hospital volume mandates
India 11.8% CAGR (2026–2035) Diagnosed pool expansion, tiered pricing
Japan USD 1.32 Billion Chuikyo rapid listing, high specialist density
South Korea 12.3% of regional revenue HIRA moderate-disease coverage extension
ASEAN USD 0.41 Billion Private insurance growth, medical tourism
Rest of Asia-Pacific 6.2% of regional revenue Australia PBS listings


China anchors regional growth in the Atopic Dermatitis Market, but the mechanism is volume-for-price rather than premium pricing. NRDL inclusion cut list prices by more than half while guaranteeing procurement across the tertiary hospital network, and manufacturers report unit volumes rising four- to sixfold within eighteen months of listing [2]. Japan's density of board-certified dermatologists — approximately 6.9 per 100,000 — sustains high diagnostic accuracy and early systemic initiation. India remains the largest untapped pool, with CDSCO approvals in place but reimbursement still overwhelmingly out-of-pocket [9].

South America

Country Metric Key Driver
Brazil 58.3% of regional revenue ANVISA approvals, CONITEC incorporation
Argentina USD 0.18 Billion Private health plan coverage
Rest of South America 9.7% CAGR (2026–2035) Chile and Colombia formulary expansion


Brazil's dual system splits the opportunity cleanly: supplementary health plans covering roughly 51 million lives fund most biologic use, while CONITEC incorporation into SUS remains slow and severity-gated. Argentina's inflation environment has pushed manufacturers toward hard-currency contracting and shorter tender cycles. Across the region, patient assistance programs rather than public reimbursement drive the majority of first fills [19].

Middle East & Africa

Country Metric Key Driver
Saudi Arabia 31.2% of regional revenue Vision 2030 healthcare privatization
UAE USD 0.16 Billion Mandatory insurance, expatriate specialist supply
South Africa 14.5% of regional revenue Private medical scheme coverage
Egypt 10.4% CAGR (2026–2035) Universal Health Insurance rollout
Rest of MEA USD 0.19 Billion Tender-based procurement


Gulf states convert wealth into access faster than any other emerging bloc. Saudi Arabia's Health Sector Transformation Program allocated substantial capital to specialty outpatient capacity, and the Saudi FDA now recognizes EMA and FDA approvals through an abridged pathway [20]. Egypt's phased Universal Health Insurance rollout, targeting national coverage by 2032, represents the region's largest structural opportunity, though current formularies remain steroid-dominant.


Atopic Dermatitis Market By Region, 2025-2035

Competitive Benchmarking

Concentration is medium. The Herfindahl-Hirschman Index (HHI) for the Atopic Dermatitis Market is projected to be around 1,150, with the top five players accounting for around 58–63% of the global market’s revenue share. That structure is a barbell, with two dominating biologic franchises flanking a lengthy tail of topical and generic manufacturers competing on price. Barriers are going up when outcomes-based contracting promotes evidence infrastructure over molecular counting.

Company Est. Revenue Share Range Key Offerings for Atopic Dermatitis Market Strategic Positioning
Sanofi ~22–26% IL-4Rα biologic franchise, pediatric formulations Category leader; broadest age-range label
Regeneron Pharmaceuticals ~14–18% Co-developed IL-4Rα biologic, OX40L pipeline Discovery engine; profit-share economics
AbbVie ~8–11% Oral JAK inhibitor, topical portfolio Immunology cross-selling scale
Pfizer ~6–9% Oral JAK inhibitor, topical PDE-4 agent Dual-modality mild-to-severe coverage
Eli Lilly ~4–6% IL-13 selective biologic Ex-US commercialization focus
LEO Pharma ~4–6% IL-13 biologic, topical dermatology range Dermatology pure-play specialist
Incyte ~3–5% Topical JAK cream Non-steroidal topical leadership
Galderma ~3–5% IL-31 biologic, barrier repair emollients Itch-pathway differentiation
Amgen ~2–4% OX40 receptor antagonist (late-stage) Next-wave mechanism entrant
Organon ~2–4% Topical AhR agonist Non-steroidal maintenance niche
Bausch Health ~1–3% Topical corticosteroid and calcineurin portfolio Value-tier volume supplier
Otsuka Pharmaceutical ~1–3% Topical PDE-4 agent, Japan portfolio Regional depth in Asia-Pacific


Recent News & Developments

  • Sanofi and Regeneron (June 2024): Reported Dupixent quarterly net sales exceeding USD 3.5 billion, with dermatology contributing the largest indication share — confirming biologic durability in the category [3]
  • FDA (December 2024): Approved a topical aryl hydrocarbon receptor agonist for mild-to-moderate disease in patients aged two and above, opening the non-steroidal maintenance segment [12]
  • National Healthcare Security Administration, China (December 2023): Completed NRDL negotiation adding interleukin-targeted dermatology agents at negotiated discounts above 55%, triggering a step-change in Chinese volume [2]
  • Galderma (February 2025): Secured EU marketing authorization for its IL-31 receptor antagonist, establishing a distinct pruritus-first mechanism in the European market [21]
  • Amgen and Kyowa Kirin (September 2024): Reported positive Phase III topline data for their OX40 receptor antagonist, supporting a 2026 regulatory submission timeline [22]
  • LEO Pharma A/S (December 2025): LEO Pharma A/S has submitted a label extension application to the European Medicines Agency (EMA) to extend the use of Anzupgo (delgocitinib) cream to teenagers aged 12 to 17 years with moderate to severe chronic hand eczema in the EU.
  • FDA (December 2024): FDA approved Vtama (tapinarof) cream (1%) for the treatment of . Vtama is a nonsteroidal topical therapy from Dermavant, an Organon business.


Atopic Dermatitis Market Report Scope

Parameter Detail
Market Scope Global prescription and non-prescription therapeutics for atopic dermatitis across drug class, route of administration, patient age group, distribution channel and geography
Study Period 2021–2035 (Historical 2021–2024; Base Year 2025; Forecast 2026–2035)
CAGR 8.9% (2026–2035)
Market Size Checkpoints USD 20.69 Billion (2025); USD 22.53 Billion (2026); USD 48.53 Billion (2035)
Fastest Growing Segments JAK inhibitors and biologics (drug class); injectables (route); pediatric (age); online and tele-dermatology (channel)
Companies Profiled Sanofi, Regeneron Pharmaceuticals, AbbVie, Pfizer, Eli Lilly, LEO Pharma, Incyte, Galderma, Amgen, Organon, Bausch Health, Otsuka Pharmaceutical
Valuation Currency USD Billion, constant 2025 dollars

FAQs

How should investors evaluate assets entering the Atopic Dermatitis Market before Phase III readout?
Weight the mechanism against remission durability, not just EASI-75 rates. Assets promising drug-free intervals command premium payer interest because they lower lifetime cost per patient [4].
What procurement terms should hospital formulary committees negotiate for dermatology biologics?
Push for outcomes-linked rebate tiers keyed to week-16 response, plus volume-independent pricing floors. Wastage clauses matter for weight-banded pediatric dosing, where partial-vial discard erodes budget quickly [16].
Which competitive dynamic in the Atopic Dermatitis Market is most underestimated?
Switching friction. Once a patient stabilizes on a biologic, dermatologists rarely change agents absent loss of response, so early market entry compounds far more than efficacy rankings suggest [7].
How do IL-13 selective agents differ practically from IL-4Rα blockers?
IL-4Rα blockade inhibits both IL-4 and IL-13 signaling; selective IL-13 agents spare the IL-4 arm. Conjunctivitis rates differ meaningfully between them, which shapes prescriber preference [25].
What regulatory nuance most affects launch sequencing in the Atopic Dermatitis Market?
Pediatric investigation plan timing. EMA requires an agreed plan before adult filing, so sponsors deferring pediatric commitments face European delays that US filings do not impose [6].
Are there emerging use cases beyond moderate-to-severe disease?
Prevention of the atopic march is the most credible frontier. Early barrier-directed intervention in high-risk infants is under active study for reducing subsequent asthma incidence [24].
What integration challenges arise when adding tele-dermatology to specialty distribution?
Prescription routing conflicts with limited-distribution networks are the main friction. Benefits verification and cold-chain handoffs also need rebuilding, since platform pharmacies rarely carry existing specialty accreditation [14].    
Author
Author
Author Profile
Nidhi Mandole LinkedIn Senior Research Analyst
She is an extremely curious individual currently working in Healthcare and Medical Devices Domain. Nidhi is comfortably versed in data centric research backed by healthcare educational background. She leverages extensive data mining and analytics tools such as Primary and Secondary Research, Statistical Analysis, Machine Learning, Data Modelling. Her key role also involves Technical Sales Support, Client Interaction and Project management within the Healthcare team. Lastly, she showcases extensive affinity towards learning new skills and remain fascinated in implementing them.
Co-Author
Co-Author Profile
Rahul Gotadki LinkedIn Research Manager
He holds an experience of about 9+ years in Market Research and Business Consulting, working under the spectrum of Life Sciences and Healthcare domains. Rahul conceptualizes and implements a scalable business strategy and provides strategic leadership to the clients. His expertise lies in market estimation, competitive intelligence, pipeline analysis, customer assessment, etc.

Research Approach


Secondary Research

The secondary research process involved comprehensive analysis of regulatory databases, peer-reviewed medical journals, clinical trial repositories, and authoritative health organizations. Key sources included the US Food & Drug Administration (FDA), European Medicines Agency (EMA), Pharmaceuticals and Medical Devices Agency (PMDA) of Japan, and National Medical Products Administration (NMPA) of China. Clinical and epidemiological data were gathered from the National Institute of Allergy and Infectious Diseases (NIAID) Atopic Dermatitis Research Network (ADRN), Centers for Disease Control and Prevention (CDC), World Health Organization (WHO) Global Health Observatory, and National Institutes of Health (NIH) PubMed/MEDLINE database.

Professional dermatology and allergy organizations provided clinical guidelines and treatment protocols, including the American Academy of Dermatology (AAD), European Academy of Dermatology and Venereology (EADV), International Eczema Council (IEC), European Dermatology Forum (EDF), and European Task Force on Atopic Dermatitis (ETFAD). Real-world evidence and post-marketing surveillance data were extracted from the TREAT Registry Taskforce (Treatment of ATopic Eczema Registry), CorEvitas Atopic Dermatitis Registry, SECURE-AD global registry, and ClinicalTrials.gov. Epidemiological statistics were validated through the International Study of Asthma and Allergies in Childhood (ISAAC), National Eczema Association (NEA) databases, and peer-reviewed journals including the Journal of Allergy and Clinical Immunology, Journal of Investigative Dermatology, and British Journal of Dermatology. These sources were used to collect prescription data, drug safety profiles, regulatory approval timelines, epidemiological trends, and competitive landscape analysis for biologics (IL-4/IL-13 inhibitors, IL-31 inhibitors), topical corticosteroids, calcineurin inhibitors, phosphodiesterase-4 (PDE4) inhibitors, and emerging Janus kinase (JAK) inhibitors.


Primary Research

Qualitative and quantitative insights were obtained by interviewing supply-side and demand-side stakeholders during the primary research process. From pharmaceutical and biotechnology manufacturers, supply-side sources encompassed CEOs, Chief Medical Officers, Global chiefs of Immunology/Dermatology, Presidents of Specialty Care units, Heads of Clinical Development, regulatory affairs chiefs, and market access directors. Atopic dermatitis clinical trial principal investigators, medical directors of specialty pharmacy benefit managers, formulary decision-makers, specialty pharmacists from academic medical centers, dermatology clinics, and managed care organizations, allergists/immunologists, and board-certified dermatologists (pediatric and adult) comprised demand-side sources. Market segmentation was validated across drug classes (biologics vs. small molecules), product pipeline timelines for late-stage assets were confirmed, and insights on clinical adoption patterns of systemic therapies, pricing and reimbursement strategies, patient access programs, and treatment pathway dynamics in moderate-to-severe versus mild disease were gathered through primary research.

Primary Respondent Breakdown:

• By Designation: C-level Executives (38%), Director Level (30%), Others (32%)

• By Region: North America (38%), Europe (25%), Asia-Pacific (32%), Rest of World (5%)


Market Size Estimation

Global market valuation was derived through revenue mapping and prescription volume analysis. The methodology included:

• Identification of 35+ key manufacturers across North America, Europe, Asia-Pacific, and Latin America specializing in immunology and dermatology therapeutics

• Product mapping across biologics (IL-4/IL-13 inhibitors, IL-31 inhibitors), topical corticosteroids, topical calcineurin inhibitors, PDE4 inhibitors, and oral JAK inhibitors

• Analysis of reported and modeled annual revenues specific to atopic dermatitis portfolios, including both branded and biosimilar franchises

• Coverage of manufacturers representing 75-80% of global market share in 2024

• Extrapolation using bottom-up (prescription volume × average selling price by country/region) and top-down (manufacturer revenue validation) approaches to derive segment-specific valuations across drug classes, routes of administration (topical, oral, injectable), and severity grades (mild, moderate, severe)

Download Free Sample

Kindly complete the form below to receive a free sample of this Report

Download PDF ×

We do not share your information with anyone. However, we may send you emails based on your report interest from time to time. You may contact us at any time to opt-out.